

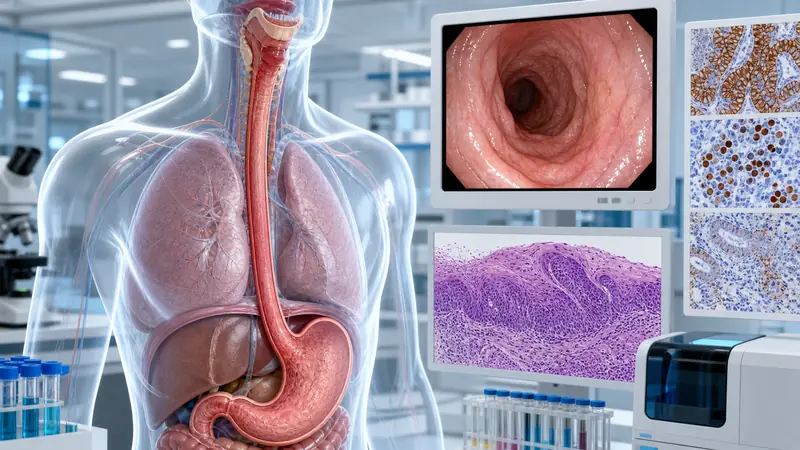
Tumor Type, Location and Stage Change the Treatment Path
Most esophageal cancers are either adenocarcinoma or squamous cell carcinoma. Adenocarcinoma commonly develops in the lower esophagus or near the gastroesophageal junction, while squamous cell carcinoma can arise throughout the esophagus. The pathology, tumor grade and precise location matter because the diseases do not always behave or respond in the same way.
Staging may include endoscopy with biopsy, endoscopic ultrasound, CT and PET-CT. The depth of tumor invasion, lymph-node involvement, relationship to nearby structures and presence of distant spread determine whether treatment is endoscopic, surgical, multimodal or primarily systemic. For advanced adenocarcinoma, HER2, PD-L1, mismatch repair or MSI and other biomarkers may affect treatment choices.
Endoscopic Treatment May Be Possible
High-grade dysplasia and selected very early cancers may be treated with endoscopic resection or surgery after careful staging.
Curative Treatment Often Uses More Than One Modality
Surgery alone may be used in selected early cases; many patients receive chemotherapy or chemoradiation before surgery.
Chemoradiation May Be Definitive or Preoperative
Histology, location, resectability, health and response help determine whether surgery follows chemoradiation.
Biomarkers and Symptom Relief Matter
Chemotherapy, immunotherapy, targeted treatment, clinical trials and procedures to relieve swallowing problems may all be considered.
Support the Person Without Delaying Potentially Curative Care
Esophageal cancer treatment may include endoscopic resection, esophagectomy, chemotherapy, radiation, immunotherapy, targeted medicine, a clinical trial or a combination of these approaches. Early and locally advanced disease may still be treated with curative intent. A natural or integrative plan should not interfere with the timing of staging, nutrition support, chemoradiation or surgery.
Sunridge reviews the pathology, scans, endoscopic findings, biomarkers, laboratory trends, weight trajectory, swallowing ability, medications, supplements, previous treatment and current goals. We can help identify supportive priorities, interaction risks and measurable points for reassessment while the oncology plan moves forward.
Natural Therapies Can Support Resilience When They Are Carefully Coordinated
Interest in nutrition and natural medicine is welcomed. Selected approaches may support nausea, stress, sleep, activity and overall quality of life. But supplements can affect bleeding, anesthesia, liver metabolism and the action of chemotherapy or radiation. High-dose antioxidants and concentrated botanicals need individual review for evidence, timing and interaction risk.
Swallowing, Weight and Muscle Need Early Attention

Difficulty swallowing, painful swallowing, early fullness, reflux, nausea and treatment effects can reduce intake. An individualized support plan may address:
- Texture-modified, energy-dense and protein-rich foods
- Hydration and electrolyte needs
- Weight loss and preservation of lean body mass
- Swallowing and aspiration assessment
- Feeding-tube questions when oral intake is inadequate
- Nausea, reflux, taste changes and bowel symptoms
- Safe conditioning before and after surgery
- Review of every herb, supplement and high-dose nutrient
NCI’s nutrition guidance emphasizes that nutritional status can affect treatment tolerance. Swallowing rehabilitation and postoperative exercise may help selected patients, although the esophageal-cancer evidence base is still developing and programs should be supervised. Speech-language pathology, oncology nutrition, surgery and rehabilitation referrals can be as important as any supplement.
When Patients Come to Sunridge
Before Chemoradiation or Surgery
We can review nutrition, weight, conditioning, swallowing, supplement risks and recovery priorities without delaying time-sensitive care.
During Active Treatment
Care may focus on intake, hydration, nausea, fatigue, pain, stress, sleep and screening natural products for interactions.
After Esophagectomy
Recovery may include smaller meals, reflux and dumping-symptom strategies, swallowing rehabilitation, respiratory conditioning and rebuilding strength.
With Recurrent or Metastatic Disease
We reassess histology, biomarkers, prior response, swallowing, organ function and goals before discussing additional support.
What We Review
Helpful records include the endoscopy and pathology reports, tumor location, histology and grade, endoscopic ultrasound findings, PET-CT and other imaging, operative and radiation reports, chemotherapy and immunotherapy history, HER2, PD-L1 and MMR/MSI results when available, current laboratory values and a complete medication and supplement list.
We also want to understand what foods and liquids can be swallowed, recent weight and muscle loss, aspiration concerns, pain, reflux, nausea, fatigue and the goals that matter most. Those practical details help shape a plan that is medically coherent and livable.
Questions About Integrative Esophageal Cancer Care
Do you treat Stage 4 or metastatic esophageal cancer?
Yes. Recommendations depend on histology, biomarkers, metastatic sites, prior treatment, swallowing, nutritional status, symptoms, organ function and personal goals. Integrative support is coordinated with the oncology plan.
Can I come while receiving chemotherapy, radiation or immunotherapy?
Potentially. Many patients seek supportive care during active treatment. Every supplement and therapy must be reviewed for bleeding, drug interactions, immune effects, radiation timing, nutrition and surgical plans.
What is the difference between adenocarcinoma and squamous cell carcinoma?
They arise from different cell types and often occur in different parts of the esophagus. Histology can affect staging details, treatment choices, biomarkers and expected patterns of response.
Can natural therapies replace surgery or chemoradiation?
No natural therapy has been proven to replace potentially curative esophageal-cancer treatment. Integrative approaches may support selected symptoms, strength and quality of life. Sunridge explains what is supported, what is uncertain and where delay could carry meaningful risk.
Can you help if I am losing weight or struggling to swallow?
Yes, but rapidly worsening swallowing requires prompt evaluation. Support may include coordinated nutrition, texture modification, symptom management and referral for swallowing assessment, endoscopic intervention or feeding support when needed.
Will you work with my oncologist, radiation oncologist and surgeon?
Yes. Communication among the treating specialists helps reduce conflicts and keeps the full plan coherent.
References
- National Cancer Institute. Esophageal Cancer Treatment.
- National Cancer Institute. Esophageal Cancer Treatment by Stage.
- National Cancer Institute. Esophageal Cancer Treatment (PDQ®)–Health Professional Version.
- National Cancer Institute. What Is Esophageal Cancer?
- National Cancer Institute. Nutrition in Cancer Care (PDQ®).
- National Cancer Institute. Cancer Therapy Interactions With Foods and Dietary Supplements (PDQ®).
- Society for Integrative Oncology–ASCO guideline for anxiety and depression symptoms in adults with cancer.
- ASCO–Society for Integrative Oncology guideline update for cancer-related fatigue.
- Exercise-based dysphagia rehabilitation for adults with esophageal cancer: systematic review.
- Nutritional-management experiences and needs in esophageal cancer: systematic review and qualitative meta-synthesis.
- Exercise and quality of life after esophageal or gastric cancer surgery: systematic review and meta-analysis.
This page is educational and does not replace diagnosis or treatment advice from a qualified medical professional. Treatment outcomes cannot be guaranteed.