

Does breast itching matter more because of how intensely it itches, or because of where it starts and how the skin changes? Location, whether one or both breasts are affected, duration, and visible changes usually offer more useful clues than itch intensity alone.
Most causes of itchy breasts involve irritated or inflamed skin, not cancer. Still, a persistent nipple change or a rapidly swollen breast shouldn't be treated as an ordinary rash without examination. Understanding the pattern helps patients choose an appropriate next step without assuming either the worst or that nothing needs attention.
Table of Contents
- Common Causes of Itchy Breasts at a Glance
- Skin Conditions Behind Most Breast Itching
- Hormonal Changes and Infections That Cause Itching
- Itch Without a Visible Rash
- Paget Disease and Inflammatory Breast Cancer Explained
- Red Flags That Mean Prompt Evaluation
- How a Clinician Evaluates Breast Itching
- Deciding When to Book a Breast Evaluation
Common Causes of Itchy Breasts at a Glance
Breast itching usually begins in the skin rather than deeper breast tissue. Dryness, sweat, friction, and inflammatory skin conditions can all produce similar sensations, including itching, burning, cracking, or tenderness. Common conditions are often manageable, but their appearance can overlap with problems that require breast-focused evaluation.
The useful distinction isn't only rash versus cancer. It's whether symptoms follow a recognizable exposure, improve when that exposure stops, or instead persist and progressively change. The National Cancer Institute's guidance on Paget disease describes nipple itching, redness, crusting, and thickening among the changes that can resemble a skin condition.
Common causes of itchy breasts and their typical pattern
| Cause | Where itching usually occurs | Typical course | Usual concern level |
|---|---|---|---|
| Contact dermatitis from soaps, detergents, lotions or fabrics | Skin touching the product or fabric, often under the bra | Improves after the trigger is removed | Usually low |
| Atopic dermatitis (eczema) | Breast skin, which can include the areola | Recurring flares with dryness and scaling | Usually low; can involve the areola |
| Fungal intertrigo or candidiasis | Inframammary fold, the skin under the breast | Redness and moisture, worse in heat and sweat | Usually low; evaluate if persistent |
| Psoriasis | Breast skin, sometimes with well-defined plaques | Chronic, with flares and remissions | Low to moderate; needs confirmation |
| Scabies | Skin folds and areas around the breast | Persistent itching that may affect others in the household | Usually low; needs specific treatment |
| Mastitis or breast infection | One localized area of the breast | Warmth and tenderness, sometimes fever | Requires prompt medical care |
| Paget disease of the breast | Nipple or areola, often first | Persistent scaling, crusting, burning or discharge | Requires prompt evaluation |
| Inflammatory breast cancer | Whole breast, usually one side | Rapid swelling, warmth, thickening or orange-peel skin | Requires urgent evaluation |
Nipple location alone doesn't identify the cause. A 2025 clinical guide from the Royal Australian College of General Practitioners reports that up to 20% of people with atopic dermatitis develop eczema affecting the nipple or areola, a figure describing people with atopic dermatitis generally, not people presenting specifically with breast itching.
Pattern matters: A rash that improves after avoiding a particular product offers a different clue from a nipple lesion that keeps returning despite gentle skin care.
No row in this table diagnoses an individual. A clinician considers the skin and breast together, because infection, eczema, and cancer-related changes can share visible features. Even a familiar-looking rash deserves another assessment if its behavior changes.
Skin Conditions Behind Most Breast Itching
A rash following the outline of a bra suggests a different starting point from irritation concentrated in a damp fold beneath the breast. Where the itch sits and what touches that area can help narrow the possibilities before testing.
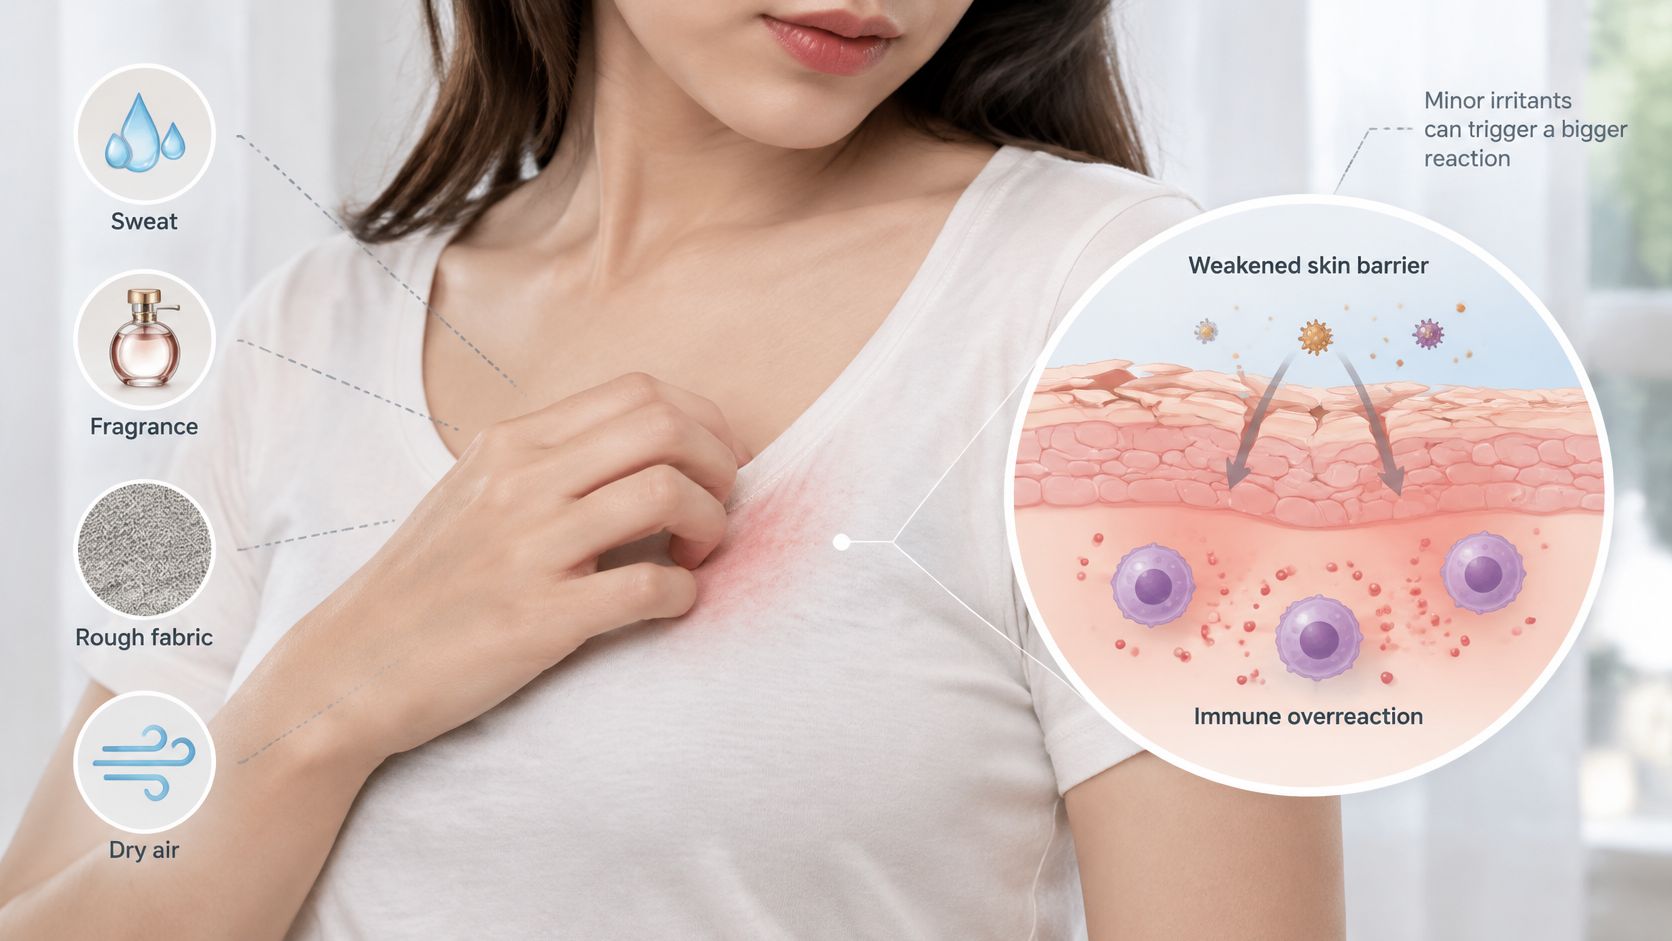
A weakened barrier can make ordinary exposures irritating
Atopic dermatitis involves immune overreaction and a skin barrier that doesn't retain moisture or protect against irritants as effectively. Genetic susceptibility and environmental exposures both contribute. Cleveland Clinic's breast eczema guidance identifies dryness, environmental triggers, and inflammation as important parts of this condition.
Low-humidity air, heat, perspiration, wool or synthetic fabrics, fragrances, harsh soaps, detergents, and personal-care products can aggravate sensitive skin. Arizona's dry conditions may make dryness a useful part of the history, but climate alone doesn't explain a persistent nipple lesion.
Contact dermatitis is related but not identical to atopic eczema. An irritant can directly damage the skin, while allergic contact dermatitis involves an immune reaction to a particular substance. A new laundry product, adhesive, lotion, or bra component may help explain the distribution, but timing alone doesn't establish an allergy.
- An exposure-shaped rash: Irritation along a bra band or beneath an adhesive supports considering contact dermatitis.
- A damp-fold pattern: Recurrent redness and moisture under the breast suggest intertrigo, sometimes complicated by yeast overgrowth.
- Distinct persistent patches: Well-defined areas of inflamed skin may suggest psoriasis rather than a reaction to a newly introduced product.
Reduce irritation without guessing at treatment
General measures include fragrance-free cleansers and moisturizers, thoroughly rinsed bras, changing out of damp clothing, and gently keeping skin folds dry. For patients examining fabric, fit, and friction, Nuage Wears offers a guide to gentler everyday intimates. Clothing changes can reduce exposure, but they don't replace assessment of a persistent rash.
Psoriasis needs a different clinical discussion from a presumed detergent reaction. The clinic's information about individualized psoriasis care provides context for patients with an established diagnosis or broader inflammatory skin concerns.
Persistent, spreading, painful, oozing, or treatment-resistant eruptions warrant examination. Eczema, fungal infection, psoriasis, and scabies can resemble one another, yet require different treatment. Repeatedly switching among steroid, antifungal, and antibacterial products without a diagnosis can also make it harder to judge what is helping.
Hormonal Changes and Infections That Cause Itching
Does the itching follow a cycle, affect one area, or come with signs of illness? Those patterns help distinguish a recurring hormonal association from a possible infection, while an examination helps clarify what is causing the symptoms.
Pregnancy, breastfeeding, menstrual changes, perimenopause, and menopause can coincide with dryness, tenderness, or altered breast sensation. Hormone therapy may also change symptoms. A recurring itch around menstruation is useful to track, but a new localized nipple change needs its own assessment, even if it appears near a period.
Timing helps distinguish a pattern from an explanation
Record when the itching starts, whether it returns around menstruation, and whether it began alongside a change in medication or hormone treatment. A clinician can compare that timeline with the examination. Breast itching alone is not a reason to start or change hormone treatment.
Pause Medical's estrogen guidance for personalized hormone care offers background for a hormone-focused discussion. For information about life-stage changes, see the clinic's guide to menopause and perimenopause.
Itching during a hormonal transition still deserves assessment when it stays in one place or comes with a new physical change.
Infection adds a different set of clues
Mastitis, which commonly occurs during breastfeeding, can cause a localized warm, tender, swollen area. Fever or flu-like symptoms add concern for infection. Breast infections can also occur outside breastfeeding.
During breastfeeding, nipple itching with discomfort or shooting pain may lead a clinician to consider yeast. These symptoms can also have other causes, so the clinician weighs the onset, examination findings, fever, and any drainage when deciding what to assess.
Hormone-associated discomfort may recur or affect a broader area, while infection may involve increasing pain or signs of illness. The pattern helps guide the evaluation, but the full history and examination matter.
Useful details for a visit include:
- Life stage: Pregnancy, breastfeeding, menstrual changes, or menopausal symptoms.
- Associated illness: Fever, chills, fatigue, drainage, or increasing tenderness.
- Treatment changes: Recently started hormone therapy, medication, supplements, or nipple products.
- Timing: Whether symptoms repeat with the cycle or follow feeding, pumping, sweating, or friction.
Itch Without a Visible Rash
Breast itching can occur without an obvious rash, bump, or discoloration. Dry skin may feel itchy before visible flaking develops, particularly in low-humidity conditions. Some medications can also be associated with itching, making a medication timeline useful.
When itching affects other areas as well, a clinician may consider causes outside the breast. Thyroid, liver, or kidney disorders and iron deficiency can be associated with generalized itch, but isolated breast itching doesn't establish any of these diagnoses. History, examination, and targeted laboratory testing help determine whether that broader evaluation is appropriate.
Details that help guide the visit
- Recent additions: Whether a medication or supplement started before the itching.
- Distribution: Whether the breasts are the only affected area.
- Other symptoms: Changes in energy, sleep, skin dryness, or general health.
- Progression: Whether the sensation is stable, spreading, or becoming more disruptive.
Broader symptoms may also prompt questions about allergic or other multisystem conditions. The clinic's discussion of histamine intolerance provides context for that separate concern, but breast itching alone doesn't establish it.
No visible rash doesn't mean no evaluation is needed. Persistent unexplained itching deserves review, particularly when it remains confined to one breast.
An examination can reveal subtle findings that aren't apparent during a home inspection. Patients shouldn't stop prescribed medication on their own because itching began after starting it; the prescribing clinician can assess the possible connection.
Paget Disease and Inflammatory Breast Cancer Explained
The absence of a lump doesn't exclude every important breast condition. Paget disease and inflammatory breast cancer can present through nipple or skin changes, which is why a persistent abnormality deserves examination even when no mass can be felt.
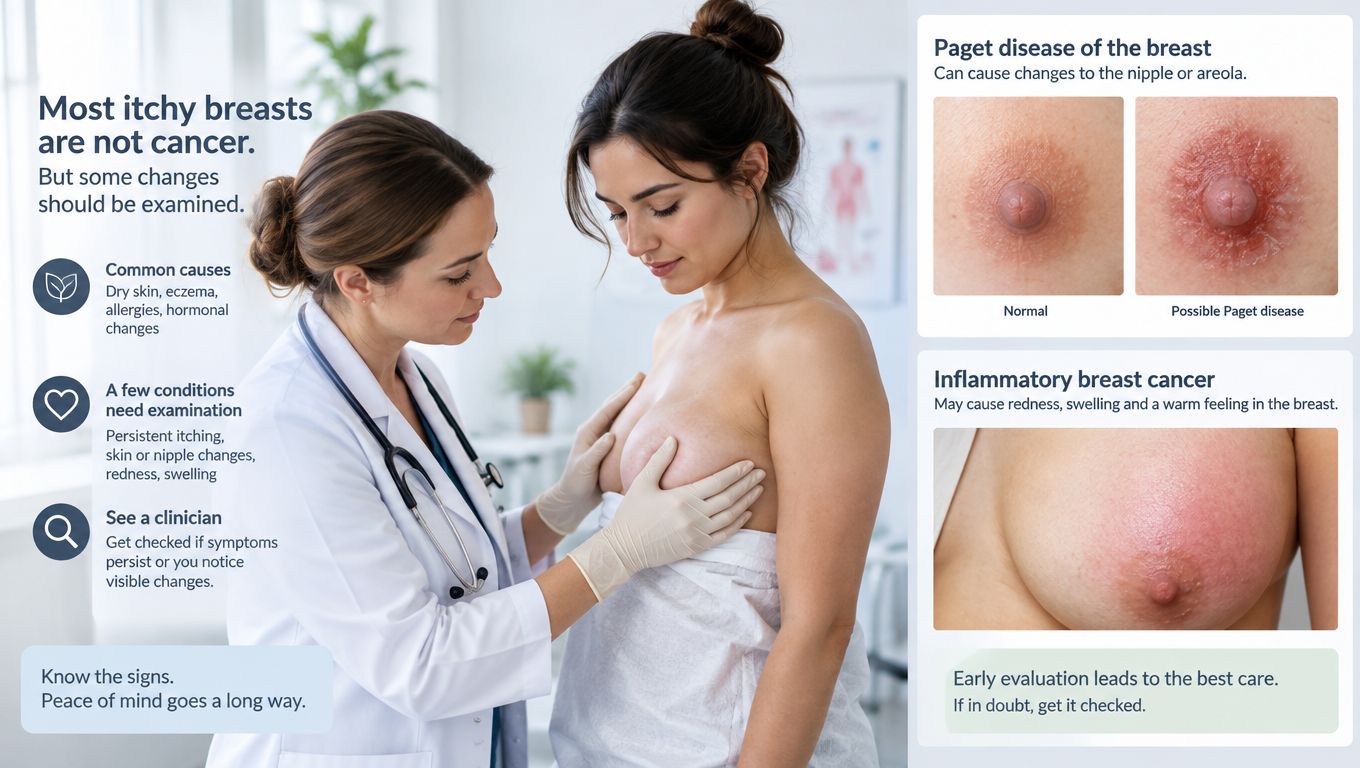
Paget disease can resemble eczema
Paget disease of the breast commonly begins at the nipple and may involve the areola. Itching, redness, scaling, crusting, burning, and discharge can look similar to dermatitis. Cleveland Clinic's explanation of itchy breasts emphasizes that uncommon cancers can imitate ordinary irritation and that persistent nipple or one-sided breast changes need evaluation.
Persistence is important. A lesion that doesn't resolve with appropriate skin care, or repeatedly returns in the same nipple, shouldn't receive another assumption of eczema. That pattern doesn't prove malignancy, but it changes the need for investigation.
Paget disease is usually associated with underlying ductal carcinoma in situ or invasive breast cancer. This connection is why clinicians evaluate the breast as well as the visible skin lesion. Treating the surface alone cannot establish what is happening underneath.
Inflammatory breast cancer changes the breast more broadly
Inflammatory breast cancer may cause rapid enlargement, warmth, heaviness, tenderness, diffuse redness or other discoloration, and skin thickening. Peau d'orange describes a pitted texture resembling orange peel. These changes occur when cancer cells obstruct lymphatic drainage in the skin.
The condition can resemble mastitis because both may produce a warm, swollen, uncomfortable breast. Fever may favor infection, but neither fever nor the absence of fever settles the diagnosis. Examination and diagnostic imaging are needed, with tissue sampling when indicated.
A discrete lump may be absent in either Paget disease or inflammatory breast cancer. Likewise, the intensity of itching doesn't reliably indicate whether the cause is benign or malignant.
- A skin finding isn't a diagnosis: Photographs and descriptions can document change but cannot replace examination.
- Imaging answers structural questions: It helps investigate the breast beneath the visible abnormality.
- Biopsy answers tissue questions: When indicated, it establishes the nature of abnormal cells.
Patients with a confirmed diagnosis or unresolved questions about an existing workup can review the clinic's information about integrative breast cancer care and second opinions. Complementary support belongs alongside, not instead of, medically necessary diagnostic and oncology care.
For an individual patient, uncertainty remains until the clinical findings and appropriate testing are considered together. Neither reassurance based on itch alone nor a cancer conclusion based on appearance is justified.
Red Flags That Mean Prompt Evaluation
Itch alone is nonspecific. Persistence, one-sided symptoms, nipple involvement, and rapid change carry more weight. A recurring nipple lesion deserves review even if it temporarily feels better after moisturizing.
Warning features and suggested timing for evaluation
| Feature | Why it matters | Suggested timing |
|---|---|---|
| Itching confined to one breast | Local irritation is possible, but unexplained one-sided change needs examination | Prompt visit; don't simply wait it out |
| Itching centered on the nipple or areola | Paget disease can begin here | Prompt visit, especially if persistent |
| No improvement after about two weeks of removing a suspected irritant | A practical review point, not a diagnostic cutoff; Mayo Clinic advises assessment of persistent breast-skin changes | Book a visit |
| Persistent scaling, crusting, oozing or burning at the nipple | Can reflect Paget disease or another skin condition | Prompt visit |
| Nipple inversion or new retraction | May signal an underlying change | Prompt visit |
| Palpable lump, thickening or skin dimpling | Requires examination and appropriate imaging | Prompt visit |
| Bloody or spontaneous nipple discharge | Needs evaluation to identify the source | Prompt assessment; same-day advice for bleeding |
| Rapid swelling, warmth, heaviness or orange-peel skin | Can indicate inflammatory breast cancer or infection | Same-day or urgent care |
| Fever with a red, painful breast | May indicate mastitis or another infection | Same-day care |
A rash that follows a clear exposure and resolves is different from a nipple-centered change that repeatedly returns. Rapid swelling, fever with a painful red breast, or bloody discharge warrants same-day clinical advice rather than waiting for a routine consultation.
Safety first: These features justify evaluation, but none proves cancer on its own.
How a Clinician Evaluates Breast Itching
Evaluation begins with the history: onset, duration, side affected, products, fabrics, medications, pregnancy or breastfeeding status, and cycle timing. A skin and breast examination then assesses the nipple, areola, fold beneath the breast, and any palpable abnormality.
Tests matched to suspected causes of breast itching
| Suspected cause | Common evaluation | What it can and cannot show |
|---|---|---|
| Contact dermatitis or eczema | Exposure history, skin examination, patch testing if allergy is suspected | Patch testing identifies contact allergens; it doesn't confirm eczema alone |
| Fungal rash or candidiasis | Skin examination, potassium hydroxide preparation or culture | Can identify fungus; a negative result doesn't identify another cause |
| Mastitis or breast infection | Clinical examination, culture when appropriate, ultrasound if an abscess is suspected | Ultrasound can locate an abscess; persistent changes may need further investigation |
| Paget disease of the breast | Biopsy of the nipple or areola lesion, with imaging | Biopsy confirms the tissue diagnosis |
| Inflammatory breast cancer | Clinical examination, diagnostic mammography or ultrasound, breast biopsy and sometimes skin biopsy | Imaging alone cannot confirm or exclude it; appropriate tissue diagnosis is needed |
| Breast mass or new skin change | Diagnostic mammography or ultrasound, biopsy when indicated | Imaging shows structure; biopsy identifies the sampled tissue |
Making the findings useful
Not every patient needs every test. Each is selected to answer a clinical question, and a negative result may leave other explanations open.
An individualized integrative evaluation can review findings alongside records from existing physicians and clarify remaining uncertainty. Standard imaging and biopsy remain central to confirming suspected breast disease; integrative care doesn't replace them.
Patients can prepare through practical guidance on participating in medical care, including bringing records and asking what each proposed test is intended to establish.
Deciding When to Book a Breast Evaluation
A stable, improving surface irritation can usually be discussed at a planned outpatient visit. Persistent or changing symptoms call for a timely appointment, with the setting guided by how quickly the symptoms are changing and whether they are affecting one or both breasts.
Match the appointment to the concern
For a mild rash that is improving, note when it began, possible product or clothing exposures, and what has helped. If it persists or returns, arrange an outpatient review. Unexplained one-sided itching, recurring nipple changes, a new lump, or skin thickening also merit an examination rather than repeated home treatment.
A symptom timeline can help focus the visit. Bring a list of products, medications, and previous treatments, along with prior breast imaging reports. Note what changed after avoiding a suspected irritant; that pattern may be more useful than rating the itch alone.
Where integrative consultation fits
Sunridge Medical, an integrative clinic in Scottsdale, can help patients from Phoenix and across Arizona review possible contributing factors and coordinate with existing physicians. Care may include appropriate skin-care, nutrition, or lifestyle support alongside standard evaluation and treatment.
If a breast specialist or oncologist is already involved, coordination helps keep care connected. An integrative appointment should not delay urgent care or medically necessary standard treatment.
Sunridge Medical offers individualized evaluation and coordinated integrative care for patients seeking clarity about persistent symptoms, including breast itching or questions about an existing breast workup. Contact Sunridge Medical in Scottsdale to discuss whether an evaluation, consultation, or second opinion may be appropriate.