


A heavy metal detox protocol should answer three questions: which exposure is relevant, whether it is affecting health, and what can be done to reduce it while supporting recovery. The answer may involve changes at home or work, nutritional and medical support, or carefully selected chelation for a confirmed poisoning. The plan depends on the metal, the route and timing of exposure, and the person’s current health.
For patients in Scottsdale, Phoenix, Paradise Valley, Tempe, Mesa, Chandler, Gilbert, and the surrounding Phoenix metropolitan area, the right starting point is a careful exposure history, appropriate laboratory testing, and an assessment of kidney function, mineral status, symptoms, and competing diagnoses. A supervised integrative evaluation can combine conventional toxicology principles with individualized nutritional and supportive care, while keeping unvalidated testing and aggressive protocols out of the decision-making process.
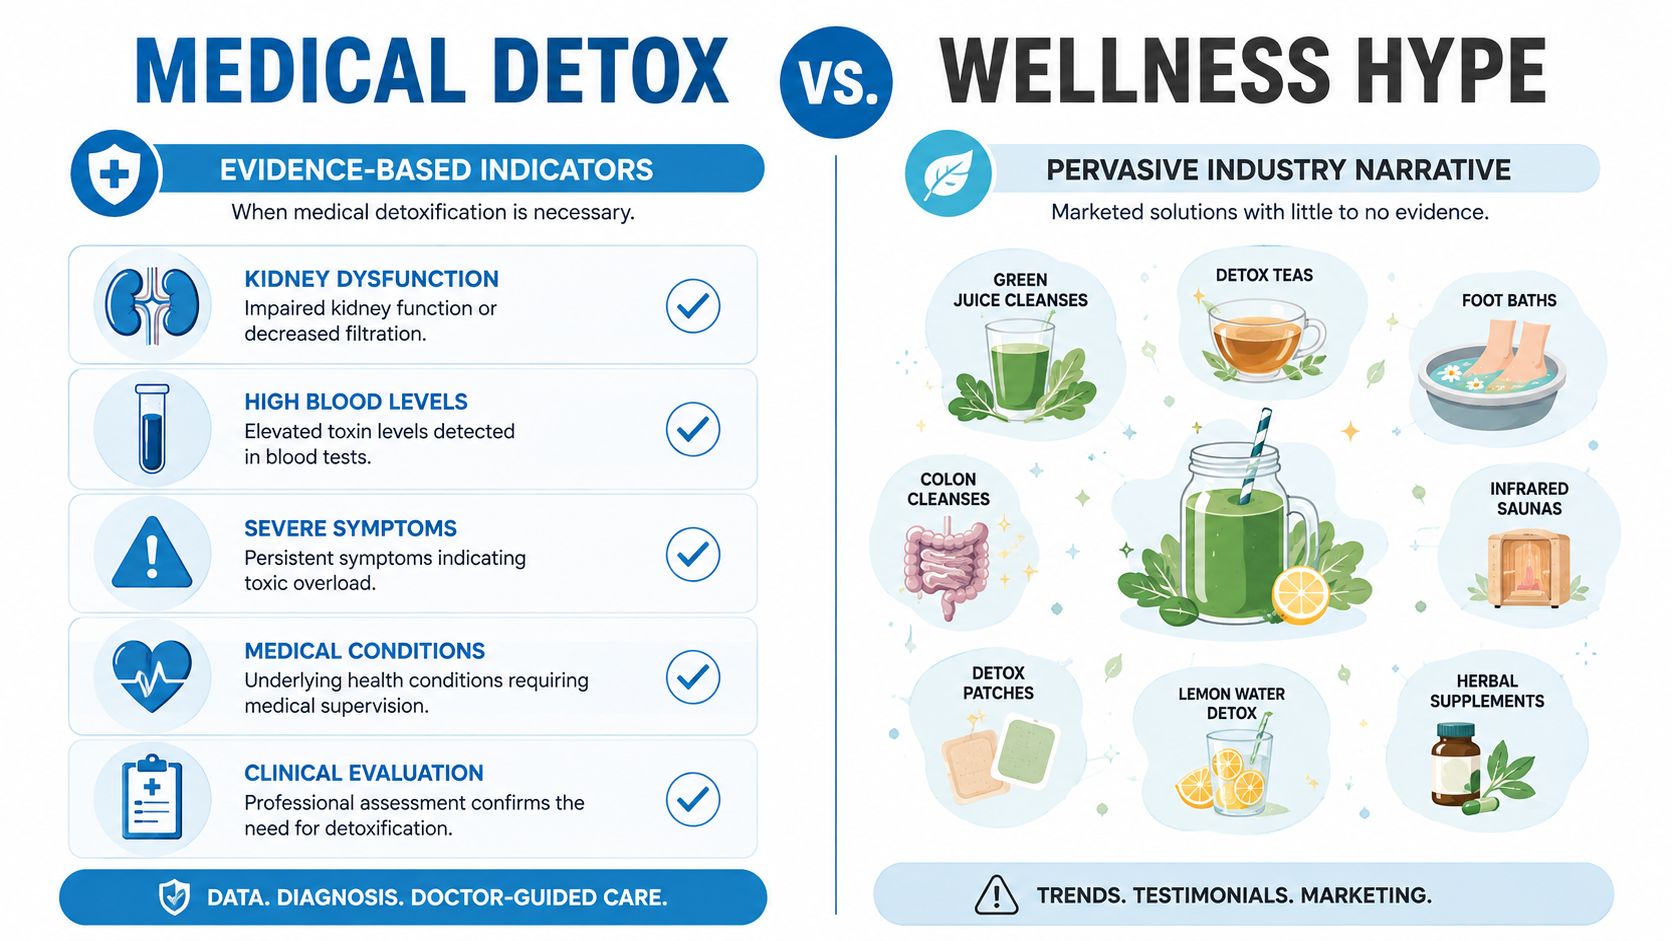
Understanding When Medical Detoxification Is Actually Necessary
Many who search for a heavy metal detox protocol don't have confirmed heavy metal poisoning. Fatigue, headaches, brain fog, digestive complaints, anxiety, or chronic pain can occur with many conditions, and symptoms alone can't establish that lead, mercury, arsenic, or another metal is responsible.
A medically relevant concern usually begins with a credible exposure and objective findings. Examples include acute lead exposure, mercury exposure related to occupational hazards or certain dental materials, or arsenic contamination. Depending on the metal and the timing of exposure, clinicians may investigate neurological changes, renal dysfunction, hematological abnormalities, or gastrointestinal distress. Those findings still require proper testing and clinical interpretation.
Exposure reduction comes before chelation
The body already uses hepatic and renal pathways to process and eliminate many substances. If a clinician identifies an ongoing source, removing or reducing that exposure is usually more important than immediately mobilizing metals. This may involve evaluating drinking water, workplace conditions, imported products, contaminated soil, food sources, or household materials.
When drinking water is a plausible source, testing and any filtration choice should match the contaminant. Water treatment can reduce a continuing exposure; it does not diagnose poisoning or replace the patient’s medical assessment.
Chelating drugs can bind essential minerals and may affect kidney function, depending on the agent and clinical situation. The choice of drug, route, treatment interval and monitoring should match the metal, exposure severity and patient. There is no universal escalation schedule or urinary-excretion target that is appropriate for every poisoning.
Practical rule: A symptom pattern can justify investigation. It can't, by itself, justify chelation.
Patients with persistent, unexplained symptoms may need a broader evaluation rather than a metal-focused protocol. For example, chronic inflammatory conditions can overlap with fatigue, cognitive complaints, and multisystem symptoms, which is why a clinical diagnostic checklist for chronic inflammatory response syndrome may be relevant to the differential diagnosis. The key question is simple: Is there confirmed toxicity, a credible exposure, and a treatment indication?
Proper Diagnostic Testing for Heavy Metal Toxicity
Testing should answer a clinical question. A broad panel that measures many elements without a relevant exposure history can produce confusing findings and encourage treatment for abnormalities that don't represent poisoning.
Choosing the specimen
The specimen should match the suspected metal and the timing of exposure. Blood lead testing is a standard tool for assessing lead exposure. Urinary arsenic with speciation can help distinguish inorganic exposure from seafood-related organic forms. Broader red-blood-cell mineral panels should not be treated as a universal diagnostic test for metal poisoning. ATSDR arsenic clinical guidance; CDC/NIOSH blood lead guidance.
Hair mineral analysis may provide supplementary information in limited contexts, but it shouldn't carry the diagnosis by itself. External contamination, laboratory methods, and interpretation can affect the result. The laboratory's reference range also needs to be considered alongside symptoms, exposure history, and other medical findings.
Provoked urine testing is different. In this approach, a chelating agent is given before urine collection, and the resulting metal concentration is interpreted as evidence of body burden. The American College of Medical Toxicology states that scientifically acceptable normal reference values haven't been established for post-challenge urine testing, and results can't be compared with standard reference ranges (ACMT position statement on post-chelator urine testing). The Oregon Medical Board likewise notes that post-chelator challenge urinary testing isn't standard of care and may be harmful. A 2020 review reports that provocative chelation testing isn't scientifically validated and was judged by ACMT to lack benefit and carry potential harm (review of chelation testing and treatment).
Heavy Metal Testing Methods Comparison
| Testing Method | Best Use Case | Clinical Validity | Limitations |
|---|---|---|---|
| Whole-blood analysis | Recent or ongoing exposure assessment | Established for selected metals when interpreted clinically | May not represent stored tissue burden for every metal |
| Unprovoked urine collection | Selected metals and ongoing excretion assessment | Useful when collection and interpretation match the exposure question | Results depend on timing, renal function, and laboratory quality |
| Hair mineral analysis | Supplementary screening and exposure context | Potentially informative as supporting evidence | Vulnerable to external contamination and interpretation errors |
| Post-chelator urine testing | Marketed as a way to reveal hidden burden | Not scientifically validated for diagnosis | Artificially increases excretion and lacks accepted normal reference values |
The testing plan should usually focus on the metal suggested by the exposure history, such as lead, mercury, arsenic, cadmium, or aluminum, rather than automatically ordering every available element. For patients seeking a broader environmental evaluation, Sunridge Medical's approach to toxic bio-accumulation describes how clinical assessment may be integrated with individualized care.
Comparing Chelation Agents and Their Clinical Applications
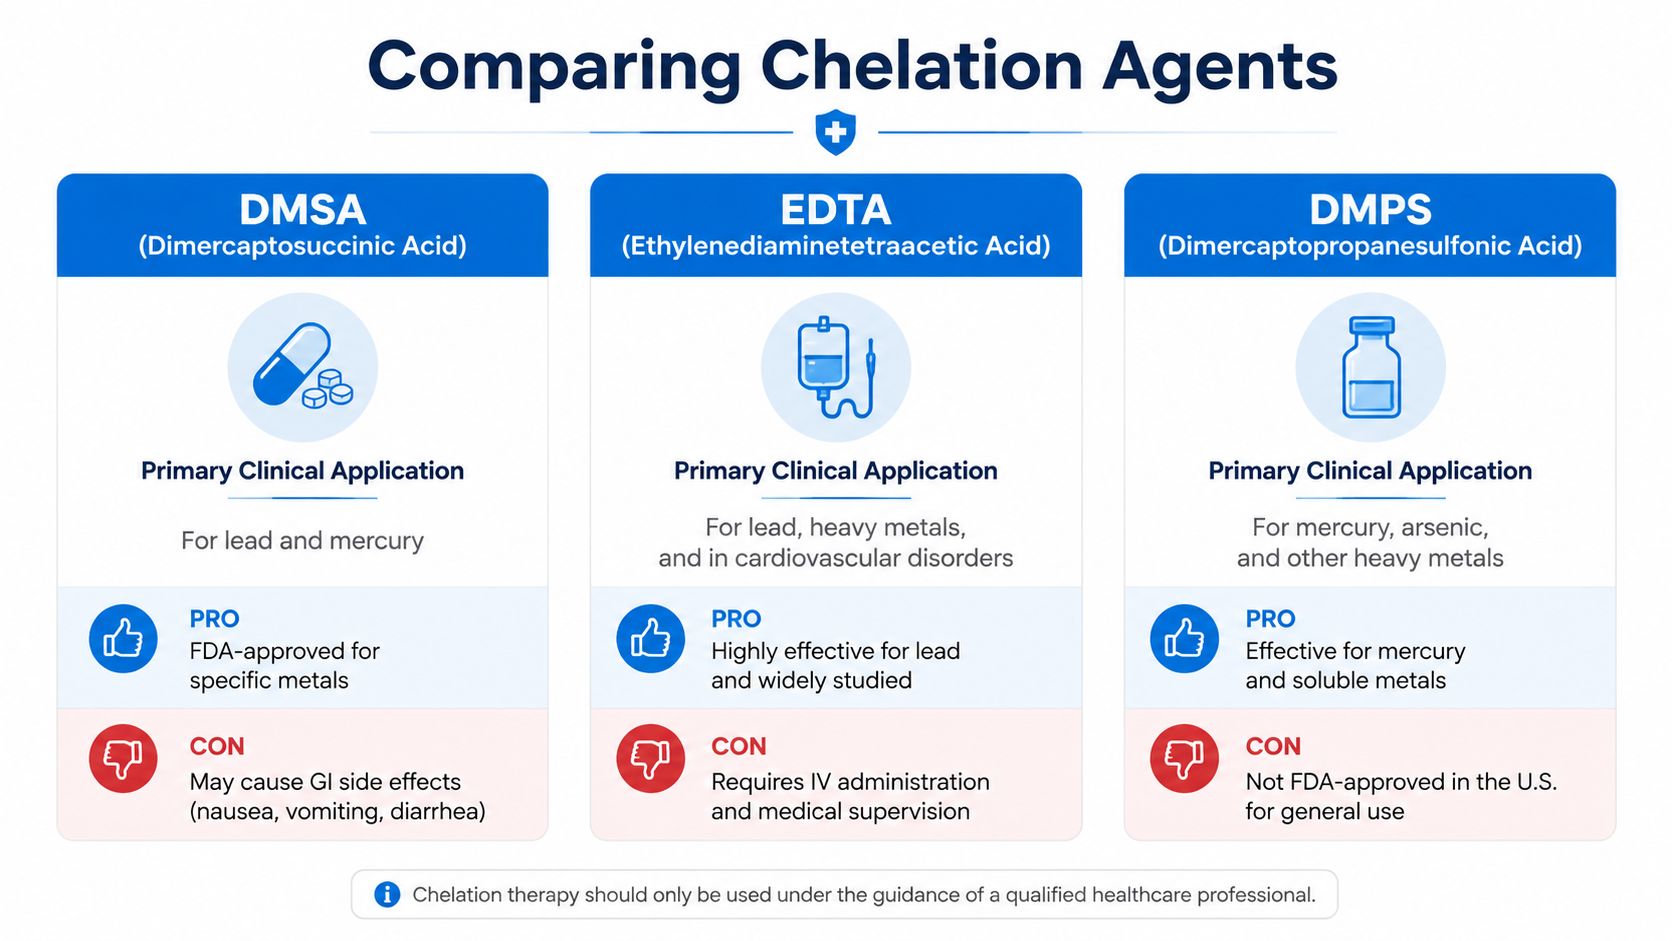
Chelators aren't interchangeable, and the phrase “heavy metal detox” can conceal important differences between medications. The agent must match the suspected metal, severity of toxicity, kidney function, symptoms, route of administration, and treatment goal.
DMSA, or meso-2,3-dimercaptosuccinic acid, is an oral chelator used in selected lead and mercury exposures. It can be practical for outpatient treatment, but oral administration doesn't make it automatically low risk. Clinicians still need to monitor tolerance, renal status, liver-related concerns, and essential minerals.
DMPS, or 2,3-dimercapto-1-propanesulfonic acid, may be considered for selected mercury and arsenic exposures. Its use depends on local clinical practice, availability, regulatory considerations, and the patient's specific circumstances. It isn't a universal solution for vague symptoms or a provoked urine result.
Calcium disodium EDTA is used in selected cases of lead poisoning under appropriate medical supervision. It must be distinguished from disodium EDTA; the formulations are not interchangeable. Drug choice and monitoring depend on the patient and the indication. FDA information on distinct EDTA formulations.
Route and risk shape the protocol
Oral and intravenous therapy involve different practical trade-offs. Oral treatment may be easier to administer, while IV therapy requires an appropriate clinical setting and offers direct administration under observation. Transdermal products and over-the-counter “detox” supplements shouldn't be treated as equivalents to prescription chelators, because their absorption, composition, and clinical evidence can differ substantially.
The metal matters as much as the medication. A 2025 review describes different antidote considerations for mercury, lead, chromium, cadmium, and arsenic, while also emphasizing that treatment includes exposure elimination, nutritional support, and supportive care, with chelation reserved for selected poisonings (recent clinical review of heavy metal toxicity management).
No chelator should be selected from a supplement advertisement or a generic online protocol. The prescription, route, dose, and monitoring plan require clinical judgment.
Implementing a Safe Medically Supervised Protocol
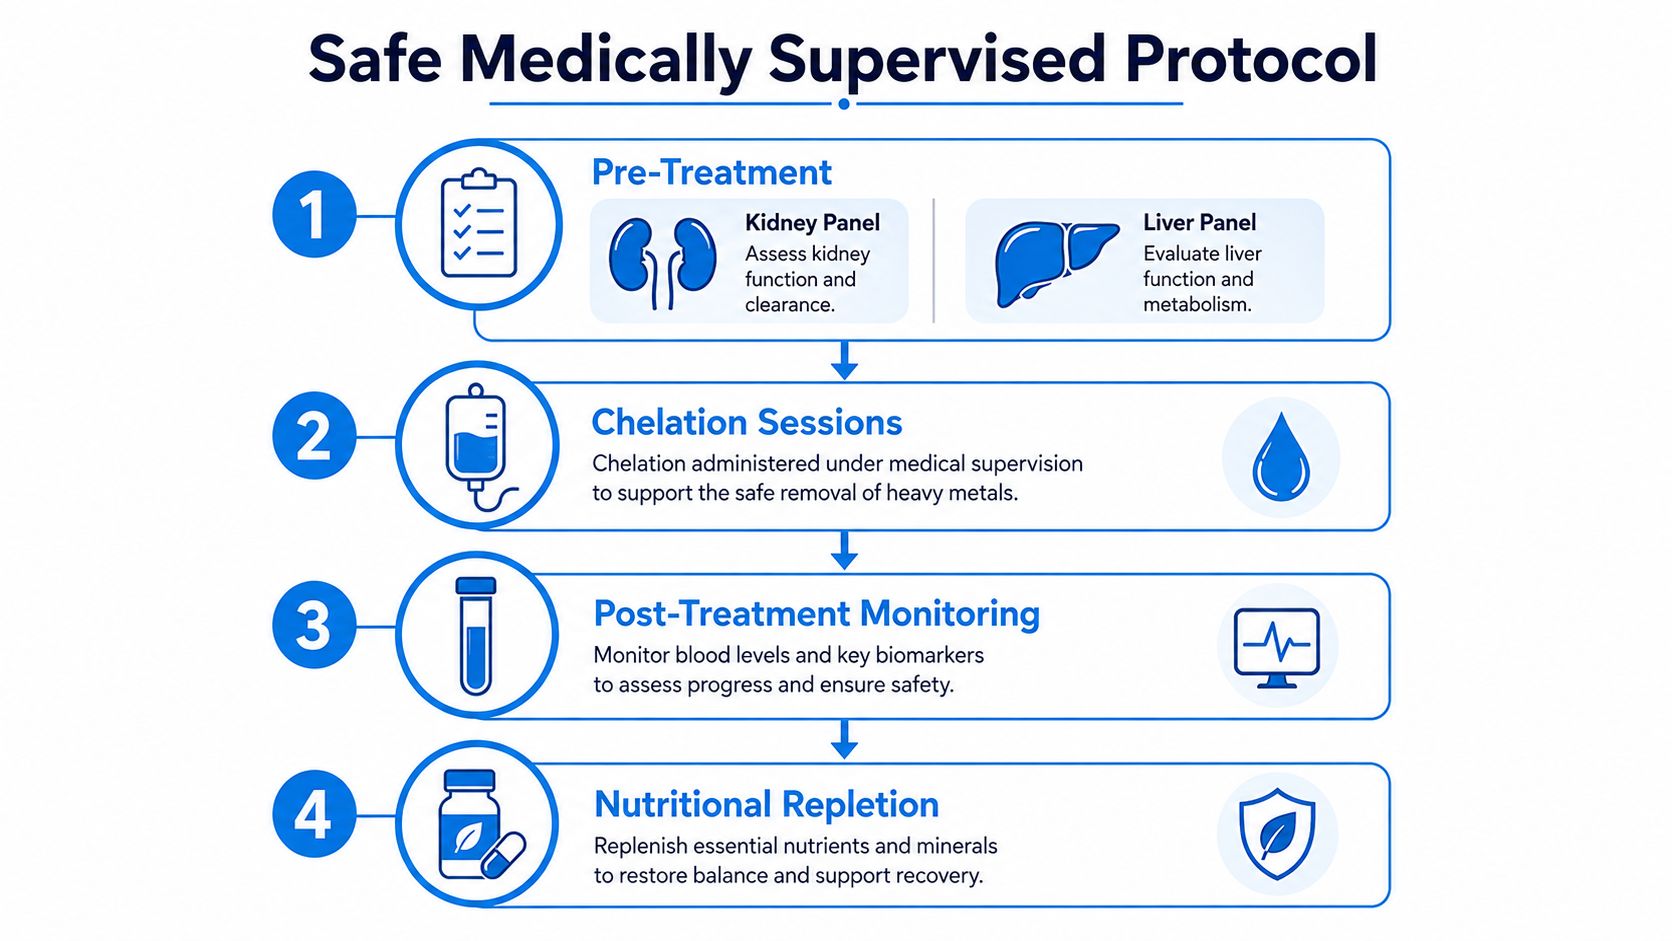
A safe heavy metal detox protocol starts before the first chelation session. The clinician reviews exposure timing, medications, allergies, pregnancy status when relevant, kidney and liver health, symptoms, hydration, and baseline mineral balance. Laboratory monitoring may include renal and hepatic measures, electrolytes, blood counts, and whole-blood or red-blood-cell essential and toxic minerals.
A cautious treatment sequence
-
Confirm the indication. The clinician connects a credible exposure with validated testing and findings that justify treatment. A positive post-chelator urine test alone isn't enough.
-
Establish a baseline. Kidney function, liver status, electrolytes, and essential minerals provide the safety reference point. The team also identifies factors that could make chelation inappropriate or require a different approach.
-
Follow the indicated regimen. Dose, timing and duration depend on the chosen drug, the metal and the patient’s condition. The clinician should establish appropriate monitoring and stopping criteria rather than follow a generic escalation schedule.
-
Reassess before repeating. Symptoms, renal status, mineral balance, exposure control, and follow-up testing inform whether treatment should continue, change, or stop. The purpose isn't to chase a higher urinary number. It's to treat confirmed toxicity safely.
Monitoring matters more than intensity. A patient who feels worse, develops abnormal laboratory findings, or loses essential minerals may need a pause or a revised plan, not a stronger dose.
Mineral supplementation should be individualized to the nutritional assessment and the chelator being used. The clinician determines the appropriate product, dose and timing so that supplementation does not interfere with treatment or create a new imbalance.
Hydration and regular bowel function support general elimination, but they don't neutralize the risks of a chelating drug. Patients shouldn't attempt IV chelation, combine prescription agents, or use aggressive oral regimens without medical oversight. Sunridge Medical describes IV therapy for environmental illness as part of a supervised clinical setting, where the broader health picture can be considered.
Supportive Therapies and Nutritional Foundations
Supportive care can improve nutritional resilience and help clinicians address the systems involved in elimination, but it shouldn't be marketed as a replacement for indicated chelation. A patient with confirmed toxicity may need exposure control, medical treatment, nutrition support, and management of the underlying condition at the same time.
A balanced diet with adequate protein, fiber, and micronutrients supports normal hepatic, renal, and gastrointestinal function. Foods containing sulfur compounds, selenium, zinc, and other nutrients may fit into a sound eating pattern, but high-dose supplements can interact with medications or worsen mineral imbalance. Clean drinking water and consistent hydration are practical foundations, especially when kidney function and fluid intake have been assessed clinically.
Adjuncts require the same skepticism
Glutathione, N-acetylcysteine, alpha-lipoic acid, selenium, modified citrus pectin, chlorella, and activated charcoal are often included in integrative detox programs. Their roles differ, and evidence for symptom improvement or metal removal isn't equivalent across products. Activated charcoal and chlorella can also affect medication absorption, so timing matters.
Infrared sauna, dry brushing, compression, and other circulation-oriented practices may be used as supportive wellness measures when appropriate. They don't directly establish toxicity, and sweating shouldn't be presented as a substitute for renal and gastrointestinal elimination or prescription chelation.

Glutathione may be administered intravenously or taken in a liposomal oral formulation, but the appropriate use depends on the patient's medical history and treatment objective. Patients considering this adjunct can review glutathione IV dosing considerations with a qualified clinician rather than selecting a dose from an online protocol.
Supportive therapy should support a diagnosis, not create one.
The most useful foundational measures are often unglamorous: reduce the exposure, eat adequately, maintain hydration, avoid unnecessary supplements, and address constipation or medication interactions. Those steps can complement medical care without claiming that every chronic symptom reflects hidden metal toxicity.
Why Professional Supervision Matters for Your Safety
Unsupervised chelation isn't a harmless experiment. Improper EDTA use can cause severe hypocalcemia, and aggressive treatment can damage the kidneys or disrupt essential minerals. A patient may also have kidney disease, liver disease, genetic differences affecting medication metabolism, or drug interactions that aren't apparent from a commercial detox questionnaire.
The FDA-approved role of chelation is treatment of metal toxicity, not general detox marketing. The CDC states that chelation generally isn't recommended for adults with blood lead levels below 45 µg/dL, and that higher-risk adults may need chelation when blood lead levels exceed 45–70 µg/dL, depending on symptoms and clinical context (CDC adult lead exposure management guidance). CSTE guidance recommends removing exposed adults from the source at 30–49 µg/dL and urgent evaluation with possible chelation when levels exceed 80 µg/dL (CSTE adult lead management guidelines). There is no established safe blood lead threshold for chronic low-level exposure in adults.
Supervised vs. Unsupervised Detox Key Safety Differences
| Factor | Medically Supervised | Unsupervised / DIY |
|---|---|---|
| Diagnosis | Exposure history and accepted testing guide treatment | Symptoms or provoked urine results may drive treatment |
| Medication selection | Agent matches the suspected metal and clinical context | Products may be combined without adequate evidence |
| Kidney and mineral safety | Baseline and follow-up monitoring can guide titration | Depletion or renal stress may go unnoticed |
| Exposure control | Clinicians identify and reduce the source | The source may remain active |
| Follow-up | Results and tolerance inform continuation or stopping | Patients may chase changing test values |
For patients in Scottsdale and the greater Phoenix area, an integrative clinic can help distinguish confirmed toxicity from other causes of chronic symptoms. Sunridge Medical offers physician-supervised environmental medicine evaluations and may incorporate chelation agents such as EDTA, DMSA, or DMPS when the clinical indication supports their use.
If you're concerned about a possible exposure or symptoms that haven't been explained, visit Sunridge Medical in Scottsdale to discuss an individualized evaluation, validated testing options, and whether medical chelation or a non-chelation approach is appropriate for you. Contact the clinic to request a consultation before starting any heavy metal detox protocol on your own.
A root-cause assessment starts with the source
An exposure timeline can be more informative than a long list of symptoms. The consultation may cover current and previous work, hobbies, home renovations, drinking-water sources, imported products, supplements and food patterns. It also asks what changed before symptoms began and whether other people sharing an environment have similar concerns.
The next step is to identify which of those details changes the clinical question. For example, private-well water may justify testing the water for a specific contaminant, while a workplace exposure may require occupational-health measures. A confirmed environmental source can guide both the patient's evaluation and practical changes that prevent continued exposure. Arsenic guidance from ATSDR emphasizes this combination of occupational, environmental and product history. (ATSDR arsenic clinical guidance)
This is where a root-cause approach becomes practical: an infusion cannot prevent the next exposure from the same source. Source control and treatment of health effects belong in the same plan.
Supporting the systems involved in recovery
A whole-person plan considers the organs and nutritional resources that treatment relies on. Kidney function matters because several metals and chelator complexes are cleared through urine. The clinician may also evaluate liver function, blood counts and mineral status according to the exposure and treatment under consideration. These findings influence what is appropriate and what needs monitoring.
Nutrition supports recovery in a more concrete way than the phrase “detox diet” suggests. Adequate food and protein intake help maintain tissue repair and normal enzyme function. Fiber, hydration within medical limits and attention to bowel symptoms support ordinary gastrointestinal function. A deficiency should be corrected thoughtfully, with attention to medication interactions and the treatment plan. A restrictive cleanse can make it harder to meet those needs.
Movement, sleep and relief of constipation or other symptoms can make an individualized plan more tolerable. Sweating practices are optional supportive measures for appropriate patients, not a substitute for exposure control or indicated treatment. Heat exposure can be a poor fit for someone with dehydration, orthostatic symptoms or relevant heart or kidney disease. IV nutrients or antioxidant support likewise need a defined clinical purpose; their use alone does not demonstrate that a metal has been removed.
Environmental medicine at Sunridge Medical
With 23+ years of practice experience and more than 24,000 patients served across the practice, Sunridge Medical offers an established setting for patients seeking a deeper evaluation of environmental contributors to illness. The consultation can connect exposure history, appropriate laboratory interpretation, nutritional needs and treatment options within one plan.
Bring previous test reports, a list of supplements and medications, and any available workplace or water-testing information. The purpose is to decide which findings deserve further investigation and whether the next step is source reduction, supportive care, a specialist consultation or medically indicated chelation. Use the consultation form to begin that individualized assessment.