

If fatigue, widespread pain, and foggy thinking can come from an infection or from a pain disorder, why do so many evaluations stop at whichever label showed up first?
A shared symptom list is only a starting point. Sorting Lyme disease fibromyalgia overlap means asking the next question in a set order, not treating a resemblance as proof. Was there a plausible tick exposure? Are there objective findings of active infection? Do the symptoms meet a clinical pain pattern after other causes are checked? If recommended treatment already finished, is another antibiotic course justified, or is coordinated symptom care the safer plan?
That sequence protects people in both directions. It can catch treatable infection that a pain label would miss, and it can also stop repeated antibiotics when the picture no longer supports active Borrelia infection. Lyme disease is an infection spread through blacklegged tick bites. Fibromyalgia is a chronic widespread-pain disorder recognized from a symptom pattern, not from one confirmatory test. The two can look alike. They aren't the same problem, and they can sometimes sit side by side in the same person.
Table of Contents
- Lyme Disease and Fibromyalgia Compared Side by Side
- Why Symptoms Overlap and Why Diagnosis Is Hard
- A Step-by-Step Evaluation to Tell Them Apart
- Reading Lyme Test Results in Context
- Persistent Symptoms After Lyme Treatment and Antibiotic Limits
- Shared Symptom Care While the Diagnosis Is Clarified
- Confirm the Right Next Step With Your Clinician
Lyme Disease and Fibromyalgia Compared Side by Side
The conditions differ in cause, in how they're confirmed, and in what an exam can see. Lyme disease begins as an infection. Fibromyalgia is diagnosed from a clinical pattern. A matching complaint list doesn't erase that difference.
| Criterion | Lyme Disease | Fibromyalgia |
|---|---|---|
| Cause | Infection with Borrelia bacteria, spread through blacklegged tick bites | Not fully established; central pain processing is a proposed mechanism |
| How it is diagnosed | Clinical assessment, with validated two-tier antibody testing when appropriate | Clinical diagnosis based on widespread pain and symptom criteria; no confirmatory lab test |
| Core symptoms | Early: rash, fever, fatigue; later may include joint, nerve, or heart involvement | Widespread pain, fatigue, sleep disturbance, and cognitive difficulty |
| Objective findings | Often present in active disease, such as rash, arthritis, or nerve involvement | Usually absent on routine laboratory testing and imaging |
| Main treatment focus | Antibiotics for confirmed active disease, as directed by a clinician | Symptom-directed, multidisciplinary care; no single standard cure |
| Shared territory | Persistent symptoms after treatment can resemble fibromyalgia | Fatigue, pain, and cognitive complaints overlap with post-treatment Lyme |
An expanding rash, a swollen joint, or a clear nerve finding points the workup toward active infection. When those findings are missing, the next job is to look for other explanations, including a primary pain disorder, rather than to stretch an infection label to fit every ache.
The two conditions can also coexist. A person can complete treatment for Lyme disease and later meet criteria for fibromyalgia. Pain, fatigue, poor sleep, and brain fog appear in both histories, which is why the lists get confused.
Practical rule: A symptom match is a question to investigate, not a diagnosis.
Readers comparing the pain pattern on its own can review how fibromyalgia is recognized as its own condition before deciding what a Lyme history does or doesn't explain.
Why Symptoms Overlap and Why Diagnosis Is Hard
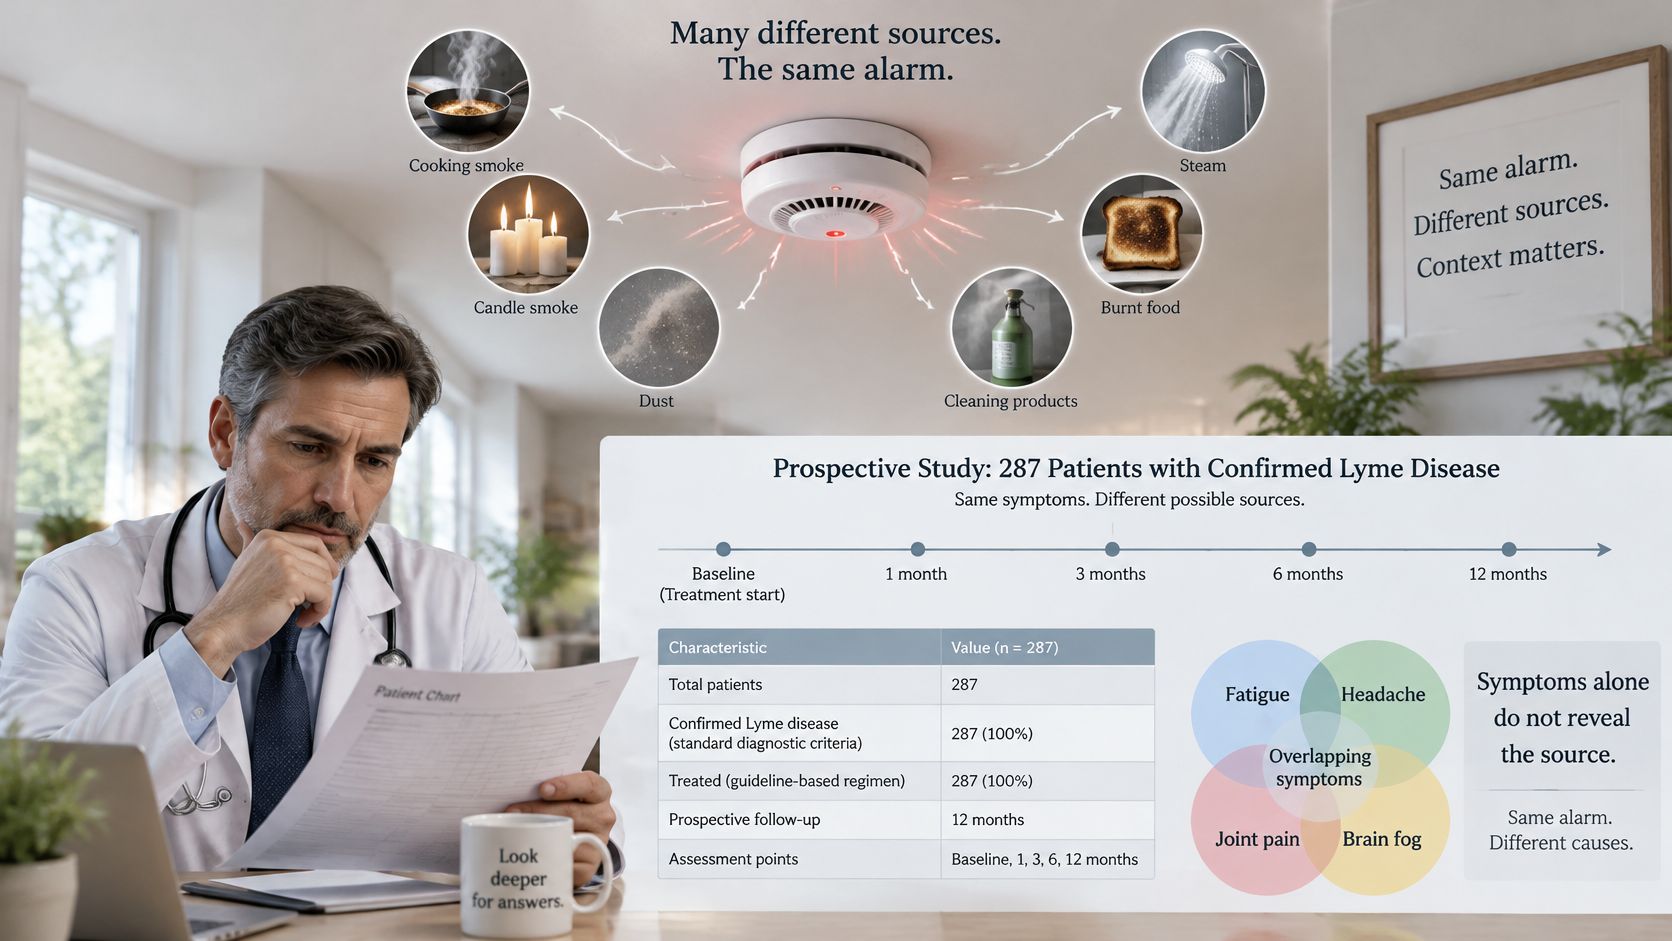
A smoke alarm doesn't name the fire. Cooking smoke, steam, dust, and a real flame can all set off the same sound. Fatigue, diffuse pain, unrefreshing sleep, and trouble concentrating work the same way. The alarm is real. The trigger still has to be found.
Diagnosis works in sequence. The first question is whether an infection is active right now. Only after that answer does it make sense to ask what else fits the pattern, because skipping the first step turns a symptom match into a label it was never built to carry.
When Lyme disease fibromyalgia labels get swapped
Timing alone does not establish cause. In a prospective study of 287 patients treated for confirmed Lyme disease, 22 people, approximately 8%, developed fibromyalgia within five months after treatment, according to a clinical review of the overlap. One condition followed the other in that subset of patients, and the study design cannot say the infection produced the pain syndrome. Persistent symptoms after treatment remain a mixed group of pain, fatigue, and cognitive complaints.
Referral clinics show the other side of the same problem. A Johns Hopkins publication reports a retrospective study of 1,261 patients sent to an academic center for suspected Lyme disease, in which 1,061 patients (84%) had no findings of active infection and fibromyalgia was identified in 120 patients (11% of the referral group), alongside a review of seven studies covering 1,902 referred patients in which only 7% to 31% had active Lyme disease and 5% to 20% had evidence of previous infection.
Population records point the same direction, and they still cannot prove cause. In an analysis of 2018 U.S. health-care data hosted by the NLM, fibromyalgia diagnoses appeared more often among people recorded as having Lyme disease in every age group from 11 through more than 70, including 16.7% of Lyme patients aged 31 to 40 compared with 1.7% of the overall patient population.
The mimic list runs long. Sleep disorders, mood disorders, thyroid disease, anemia, medication effects, and autoimmune illness can set off the same alarm, so screening for them belongs inside the evaluation itself. When the workup finds no active infection, the next step is treating whatever it did find. Repeating a therapy aimed at an infection the evidence no longer supports answers a question that was already asked.
While that workup is underway, day-to-day joint and muscle discomfort still needs practical limits on activity and recovery. Pain management guidance for active adults is one plain-language resource for staying active without treating soreness as proof of either diagnosis.
A Step-by-Step Evaluation to Tell Them Apart
A structured evaluation separates active Lyme disease, post-treatment symptoms, and fibromyalgia by sequence, so that the order of questions, rather than how closely the stories resemble each other, drives the decision. A symptom list that fits both conditions is a starting point. Some findings can't wait for the sequence at all. Fever with an expanding rash after a tick bite, facial drooping or weakness, chest pain, fainting, a racing or irregular heartbeat, swelling in one or more large joints, new numbness or weakness, or sudden confusion needs prompt conventional care.
- Exposure and timeline. Record any tick bite, including where it happened, plus travel, an earlier rash, treatment dates, and how symptoms changed afterward. Compare the bite or travel location with CDC maps of areas where Lyme disease is reported, including travel outside Arizona. A bite in a low-reporting area doesn't erase illness, and a bite in a high-reporting area doesn't confirm it.
- Symptom pattern. Note onset, duration, day-to-day fluctuation, sleep, thinking, and which daily tasks have become harder. A pattern that stays at a similar level for months is read differently from a short febrile illness.
- Objective examination. Look for joint swelling, focal neurologic signs, cranial-nerve weakness, and heart-rhythm findings. These are findings a clinician can see and measure, and they change the meaning of every test ordered afterward.
- Fibromyalgia criteria. Score the widespread pain index and the symptom-severity score using the American College of Rheumatology criteria thresholds in the table below. The score organizes the pain history. It doesn't test for Borrelia.
- Mimic screening. Sleep disorders, mood, thyroid disease, anemia, medication effects, and autoimmune markers are checked when the history points that way. Ordering every test "just in case" adds noise without answering the exposure question.
- Targeted testing. Lyme serology is used when timing and the clinical picture justify it, then read against when the illness began and what the exam found. A test ordered without that context is easy to over-read.
- Reassessment. Set a documented follow-up interval and track what changed. New joint swelling, a new neurologic sign, or a new exposure can reopen the infection question. Stable subjective symptoms call for a different plan.
The criteria are symptom-based. They don't require abnormal inflammatory markers or imaging, so a normal routine panel neither confirms nor excludes fibromyalgia. Writing down each domain, including function and any objective joint or nerve finding, keeps the reasoning visible to the patient and to other physicians.
| Criterion | Threshold | What It Means in Practice |
|---|---|---|
| Symptom duration | At least 3 months at a similar level | Separates a persistent pattern from a short illness |
| Option 1 | Widespread pain index of at least 7 and symptom severity of at least 5 | Widespread pain with moderate symptom burden |
| Option 2 | Widespread pain index of 3 to 6 and symptom severity of at least 9 | Less widespread pain with high symptom severity |
| Pain distribution | Generalized across at least 4 of 5 body regions | Required under both options |
| Inflammatory markers and imaging | Not required for the criteria | Normal routine results don't rule fibromyalgia in or out |
At Sunridge Medical, treatment recommendations depend on diagnosis, medical history, medications, laboratory findings, and physician evaluation, and no outcome can be promised.
Reading Lyme Test Results in Context
A Lyme result is a snapshot with a timestamp. It answers one question: has the immune system met Borrelia? Whether today's pain or fatigue comes from that meeting is a separate question, and it needs the exam and the timeline. Read in that order, timing first and symptoms second, the same number stops being confusing.
CDC-recommended testing is a two-step antibody process. An initial enzyme immunoassay or immunofluorescence assay comes first, and a second-tier immunoblot, or an appropriate modified two-tier assay, follows only when that first test is positive or equivocal. Both steps can use the same blood sample, and the overall result is positive only when the required first- and second-tier criteria are met. Under the standard algorithm described on the CDC diagnosis and testing page, a negative first-tier test generally means no second-tier testing is recommended. Symptom overlap with fibromyalgia doesn't replace that sequence.
What stage does to the numbers
Antibodies take time to appear. During the earliest weeks after infection, tests can be falsely negative because the immune response isn't fully developed yet. A CDC Emerging Infectious Diseases review of serologic performance puts the sensitivity of standard two-tier serology during early infection, while antibodies are still developing, at about 30% to 40%; for disseminated Lyme disease, sensitivity rises to approximately 70% to 100%, and specificity exceeds 95% when testing is performed and interpreted under current guidance.
| Test Situation | Reported Performance | What It Means for Fibromyalgia-Like Symptoms |
|---|---|---|
| Early infection, antibodies still developing | Sensitivity about 30% to 40% | A negative result may not exclude recent infection; clinical follow-up is needed |
| Disseminated Lyme disease | Sensitivity about 70% to 100% | Results carry more weight when they match objective findings |
| Specificity under current guidance | Greater than 95% when performed and interpreted correctly | A positive result still has to fit the clinical picture |
Most patients seroconvert within roughly four weeks, which is why CDC clinician guidance on serologic interpretation recommends against using an IgM-positive result alone to determine active disease once illness has lasted longer than one month: false-positive interpretation becomes more likely, and IgG generally predominates later. Months or years of fatigue, diffuse pain, poor sleep, or concentration trouble shouldn't be pinned on an isolated late IgM result.
Three questions keep the printout honest: which tiers were run, when the exposure occurred, and whether objective findings support the result.
A fuller walk-through of what Lyme disease tests can and cannot tell you helps separate the question the test answered from the question the symptoms are still asking.
Persistent Symptoms After Lyme Treatment and Antibiotic Limits
Finishing a recommended antibiotic course and still feeling unwell is a common turning point, and it raises a sequencing question: whether another course answers the problem, or whether a different question needs answering first. The assumption that more antibiotics must be the fix doesn't match how prolonged symptoms behave.
The CDC page on chronic symptoms and Lyme disease reports that, six months after recommended treatment, prolonged symptoms are approximately 5% to 10% more common among people previously diagnosed with Lyme disease than among those without it. The cause of post-treatment Lyme disease syndrome (PTLDS) remains uncertain. PTLDS can resemble fibromyalgia because both may involve widespread musculoskeletal pain, fatigue, disrupted sleep, and cognitive difficulty. That symptom match is a starting point, not a diagnosis.
Subjective symptoms can persist without active infection
Recurrent arthritis, a focal neurologic deficit, or another measurable abnormality is a different clinical problem from fatigue or pain that continues without those findings. Persistent subjective symptoms, without those objective abnormalities, shouldn't automatically be read as active Borrelia infection. Before any retreatment decision, the alternatives in a full evaluation still need a fresh look: sleep disorders, mood disorders, medication effects, endocrine disease, autoimmune conditions, anemia, and an independent fibromyalgia-spectrum disorder.
Extended antibiotic therapy has generally failed to outperform placebo for prolonged post-treatment symptoms, and it can cause harm, so repeated empiric courses aren't a default answer. These symptoms are real, and the evidence still does not support repeated antibiotics. PTLDS criteria specifically recognize function-limiting fatigue, widespread pain, or cognitive difficulty after documented Lyme disease and adequate treatment.
Coordinated care is the practical substitute.
- Physician reassessment: Recheck exposure, exam findings, and whether anything objective has changed.
- Rehabilitation referral: Graded activity and function goals, rather than rest as the only plan.
- Sleep and mood evaluation: Treat contributors that amplify pain and fatigue.
- Monitoring: Watch for signs that could indicate reinfection or another neurologic, rheumatologic, or infectious diagnosis.
Sunridge Medical may work alongside outside specialists and primary-care clinicians when coordination is appropriate for complex chronic illness. A closer look at post-treatment Lyme disease syndrome recovery and care covers how that follow-up is framed once recommended antibiotics are already done.
Shared Symptom Care While the Diagnosis Is Clarified
Care for shared symptoms can start while the cause is still being sorted. That care isn't treatment of a confirmed diagnosis, and it doesn't decide between infection and a pain disorder.
Conventional options include graded physical activity with a physical therapist, a formal sleep evaluation, mood screening and psychological support, a medication review for drugs that worsen fatigue or thinking, and clinician-directed pain management. For fibromyalgia specifically, FDA-approved medications include pregabalin, duloxetine, and milnacipran. Each has side effects and interaction risks, and each is weighed against the person's history rather than started because the symptom list looks familiar.
Integrative options can sit beside that plan. Nutrition and lifestyle support, stress-reduction practices, and a laboratory-guided review come before any supplement is considered. Supplements can interact with prescription medicines. No integrative approach replaces a confirmed diagnosis or medically necessary care, and none of these steps proves what caused the fatigue or the pain.
| Shared Symptom | Conventional Options | Integrative Options | Limits |
|---|---|---|---|
| Fatigue | Graded activity with a physical therapist; medication review | Nutrition and lifestyle support; laboratory-guided review first | Neither confirms a cause of fatigue |
| Sleep disruption | Sleep evaluation and sleep-focused strategies | Stress-reduction practices | Sleep disorders need a formal evaluation |
| Widespread pain | Clinician-directed pain management, including FDA-approved fibromyalgia medications | Stress-reduction and movement practices | Medications carry side effects and interactions |
| Cognitive difficulty | Medication review; mood screening and psychological support | Lifestyle support | Cognitive complaints need evaluation for other causes |
Sunridge Medical offers care for autoimmune conditions, complex multi-system illness, environmental illness, neurologic conditions, Lyme and tick-borne illness, digestive health, hormone and metabolic health, and fatigue, pain, and fibromyalgia. Which pieces belong in one person's plan is a clinical decision, not a menu. Non-drug approaches for pain and function are discussed further in treating fibromyalgia without medication.
Confirm the Right Next Step With Your Clinician
Deciding what to do next is a sequencing question. Two things have to be settled first: whether anything urgent is present, and whether the explanation you currently have still fits the symptoms.
If any of the warning signs listed in the step-by-step evaluation are present, seek prompt conventional or emergency care before anything else. That is the one situation where an urgent setting comes first.
A consultation or second opinion is more useful in a different set of circumstances: when symptoms remain unresolved after a standard evaluation, when two diagnoses conflict, when the open question is what care should follow a completed course of Lyme treatment, or when several conditions need one coordinated review. Guidance on when a second medical opinion makes sense and how to find the right doctor can help decide whether that kind of review fits your situation. Complex and long-standing cases are welcome at Sunridge Medical, which treats Lyme disease and tick-borne illness through individualized evaluation rather than a fixed protocol.
What to bring
- A dated symptom log: Onset, fluctuation, sleep, thinking, and what function has changed.
- Prior Lyme results with dates: Which assays were run, and how long after exposure or illness onset.
- Treatment records: Antibiotic courses, dates, and the response, including what did not change.
- Medication and supplement list: Prescription drugs and anything bought over the counter.
- Lab and imaging reports: Including normal results, which still narrow the differential.
These records do the same work the evaluation did, one level up. The timing of a Lyme test relative to exposure changes what a negative result can rule out, and a record of what failed to change on antibiotics helps your clinician decide whether repeating a course would answer anything new or whether the differential needs to widen.
Sunridge Medical offers individualized, evidence-informed evaluation for Lyme disease, tick-borne illness, fibromyalgia, and other complex symptoms that have not been clearly sorted, serving Scottsdale, Phoenix, the greater Arizona community, and patients who travel for care. A consultation can review prior testing and treatment history to see whether coordinated care is appropriate, with suitability decided only after that assessment and no outcome promised. Contact Sunridge Medical in Scottsdale to discuss whether a consultation or second opinion fits your situation.