

If stage alone decided treatment, would every person with stage 4 metastatic kidney cancer receive the same drugs, in the same order, at the same pace? That's rarely how careful oncology works. Stage describes spread, but treatment choices also depend on kidney cancer subtype, where metastases are located, symptoms, blood tests, overall function, and prior therapy. Keeping those layers separate helps patients ask sharper questions, understand survival figures without treating them as a personal forecast, and distinguish approved treatments from early research.
Table of Contents
- Stage 4 Metastatic Kidney Cancer Survival Figures Explained
- Symptoms That Need Urgent Medical Attention
- How Risk Groups and Symptoms Shape Treatment Choices
- Standard Systemic Treatments and Their Evidence
- Local Treatments When Disease Is Limited
- Options After Progression and Clinical Trial Pathways
- Integrative Therapies Compared With the Evidence
- Decide Whether a Second Opinion Fits Your Situation
Stage 4 Metastatic Kidney Cancer Survival Figures Explained
How should you read a survival percentage without treating it as a personal prediction? Start with what the category measures. In plain language, stage 4 usually means kidney cancer has spread to distant organs. The American Cancer Society summary of SEER survival data explains that the National Cancer Institute's Surveillance, Epidemiology, and End Results Program labels this category “distant” rather than stage IV. For people diagnosed with kidney or renal pelvis cancer from 2015 through 2021, the reported 5-year relative survival rate for distant disease was 19%.
A separate, more recent SEER 21 data set, covering 2016 to 2022, reports that distant disease accounted for approximately 15% of diagnosed cases and had a 5-year relative survival rate of 20.3%. Both figures describe groups, not an individual's likely course. Differences in the time period and data set also mean the estimates should not be treated as interchangeable.
Five-year relative survival by SEER stage category
| SEER category | 5-year relative survival (2015-2021) | What it means |
|---|---|---|
| Localized | 93% | Cancer confined to the kidney |
| Regional | 76% | Spread to nearby structures or regional lymph nodes |
| Distant (stage 4 metastatic) | 19% | Spread to distant organs such as lung, bone, liver or brain |
The table's figures are from the American Cancer Society summary of SEER survival data. Relative survival compares people with cancer to similar people without it. It is a population measure, not a fixed personal chance. The distant-disease group includes people with different tumor subtypes, metastatic sites, health conditions, treatments, and responses.
Time and treatment context matter, too. Survival estimates reflect people diagnosed in earlier years and may not fully represent outcomes with newer drug combinations. Clinical trials offer another perspective, though their participants may differ from patients in routine care. A 2024 review in the peer-reviewed journal Kidney Cancer reports that median survival for metastatic renal cell carcinoma can approach 47 to 55 months after extended follow-up of key treatment trials. That result applies to selected trial populations, not everyone with metastatic disease.
Practical rule: Use survival figures as background for a conversation, not as a personal prognosis.
To make the numbers relevant to your situation, ask your oncology team about your IMDC risk group, the organs involved and extent of disease, and what response, stability, or progression would look like on future scans. A guide to cancer diagnosis stages can provide broader context for understanding how stage describes the spread of cancer.
Sunridge Medical provides information for newly diagnosed patients, people with stage 4 or metastatic cancer, and those seeking a second opinion or case review. This information can support planning with the oncology team, but does not replace individualized medical advice.
Symptoms That Need Urgent Medical Attention
Guidance about symptoms supports timely care. It never replaces emergency services, urgent evaluation, or the patient's oncology team. In stage 4 metastatic kidney cancer, a new symptom can come from the cancer, a metastasis, treatment toxicity, infection, a blood problem, or an unrelated condition. The cause often can't be sorted out safely at home.
Warning signs and the appropriate level of response
| Symptom or sign | Why it matters | Appropriate response |
|---|---|---|
| Severe or sudden flank pain | May reflect bleeding or obstruction from the kidney mass | Emergency or same-day evaluation |
| Visible blood in urine | New bleeding from the tumor or urinary tract | Contact oncology promptly; emergency if heavy, clotted or with dizziness |
| Shortness of breath or chest pain | Lung involvement or other serious causes | Emergency services |
| Confusion, severe headache, weakness or seizure | Possible brain metastases | Emergency services |
| Fever, diarrhea or rash during immunotherapy | Possible immune-related side effects | Same-day call to oncology team |
| New or worsening bone pain, numbness or weakness in legs | Possible bone metastases or spinal involvement | Urgent evaluation; emergency if neurologic symptoms |
| Yellow skin or abdominal swelling | Possible liver involvement | Urgent evaluation |
| Persistent fatigue, poor appetite or weight loss | Common and often treatable contributors | Discuss at next visit; sooner if worsening |
Immune-related side effects deserve special attention because immunotherapy can trigger inflammation in organs such as the bowel, lungs, liver, skin, or hormone glands. Symptoms can begin during treatment or after a dose, and early reporting gives the team a chance to test, pause therapy, or start treatment for toxicity before the problem escalates. Waiting for the next routine visit can lose useful time.
A short record helps the clinician triage the call. Patients should note the following details before contacting the team:
- Onset and course: When the symptom started, whether it's steady or worsening, and what makes it better or worse.
- Severity: Pain level, breathlessness with activity, urine color, or number of loose stools.
- Temperature and vital signs at home: Any measured fever, dizziness, or reduced urine output.
- Medications and supplements: Cancer drugs, recent doses, antibiotics, pain medicines, blood thinners, and over-the-counter products.
Not every symptom signals an emergency. Fatigue, appetite loss, and weight change still deserve active management because they affect strength, treatment tolerance, and daily life. Pain control, nutrition support, hydration review, sleep strategies, physical rehabilitation, and medication adjustment are supportive measures that oncology and palliative care clinicians can coordinate early, alongside cancer-directed treatment.
How Risk Groups and Symptoms Shape Treatment Choices
Stage works like a map of how far disease has traveled. Risk group, symptoms, and metastatic pattern help the team decide how to steer. A weather forecast works the same way, since season alone doesn't tell a traveler whether to expect clear roads or a storm.
The International Metastatic RCC Database Consortium model, usually called the IMDC model, classifies patients as favorable, intermediate, or poor risk. The SEER Stat Facts page for kidney and renal pelvis cancer provides population context, reporting that distant-stage disease represents about 15% of kidney and renal-pelvis cancer cases. Its relative survival figure compares people with kidney cancer with similar people without cancer and remains a population estimate, not an individual prediction.

The six IMDC adverse factors
- Anemia: Low hemoglobin can reflect disease burden, inflammation, bleeding, or reduced reserve.
- Hypercalcemia: High corrected calcium may signal more aggressive disease or bone-related effects.
- Neutrophilia: High neutrophil counts can reflect systemic inflammation linked with prognosis.
- Thrombocytosis: High platelet counts are another inflammatory marker in the model.
- Reduced performance status: Limited ability to carry out daily activities affects risk and treatment tolerance.
- Short interval from diagnosis to systemic treatment: Needing treatment soon after diagnosis can indicate faster-moving disease.
The bands are simple to state. Zero adverse factors is favorable risk, one or two is intermediate risk, and three or more is poor risk. Risk group then helps shape first-line systemic therapy discussions, monitoring intensity, and how strongly certain combinations are favored.
Symptoms and lesion pattern add the next layer. NCCN patient guidance for kidney cancer states that treatment for stage 4 disease is based on symptoms and, when metastases are present, on their number and location. A hypothetical patient with one painful bone site may need discussion about local treatment for that site. A hypothetical patient with widespread asymptomatic lung and liver spread usually faces a systemic therapy decision first.
Pathology is the required first check before those choices settle. Clear-cell and non-clear-cell kidney cancers don't always follow the same treatment evidence, so the team should confirm subtype and review the original report. Sunridge Medical reviews cancer type, stage, pathology, previous treatment, molecular information when available, organ function, medications, symptoms, and individual goals before outlining treatment options.
That review approach reflects a cautious starting point. Readers considering how those pieces fit together can review how individualized cancer treatment plans are developed. Sunridge's safest starting point for cancer patients is a case review, not selecting a therapy from a list.
Standard Systemic Treatments and Their Evidence
Systemic treatment for advanced kidney cancer has shifted from a small number of options to targeted medicines and immune checkpoint combinations. An Oncologist review of treatment milestones in metastatic renal cell carcinoma describes the FDA approval of high-dose interleukin-2 in 1992 for selected patients, followed by therapies that brought more durable benefits to a broader group.
Approved and trial-supported systemic regimens for advanced kidney cancer
| Regimen | Setting | Key approval or trial evidence |
|---|---|---|
| High-dose interleukin-2 | Selected patients with metastatic disease | FDA approved 1992; early immunotherapy milestone |
| Nivolumab | Advanced disease after prior therapy | FDA approved 2015; CheckMate 025 median overall survival was 25.0 months with nivolumab versus 19.6 months with everolimus |
| Nivolumab plus ipilimumab | First-line, intermediate- or poor-risk | FDA approved April 2018; 18-month survival was 75% versus 60% with sunitinib |
| Pembrolizumab plus axitinib | First-line advanced disease | Approved 2019; KEYNOTE-426 hazard ratio was 0.53 versus sunitinib |
| Nivolumab plus cabozantinib | First-line advanced disease | Approved 2021 |
| Pembrolizumab plus lenvatinib | First-line advanced disease | Approved 2021 |
| Belzutifan | Previously treated clear-cell disease after immunotherapy and anti-angiogenic therapy | Superior efficacy to everolimus in phase 3 LITESPARK-005 |
The trial figures show how results differ by regimen and treatment setting. After prior therapy, nivolumab improved median overall survival compared with everolimus. In first-line treatment for intermediate- or poor-risk disease, the combination of nivolumab and ipilimumab had higher 18-month survival than sunitinib. These group-level outcomes help frame a discussion, but they do not predict an individual patient's course.
For pembrolizumab plus axitinib, the 2024 ESMO guideline evidence summary for renal cell carcinoma reports a hazard ratio of 0.53 versus sunitinib, with a 95% confidence interval of 0.38 to 0.74. The review also reports estimated 12-month overall survival of 89.9% versus 78.3%. A hazard ratio compares the rate of an event over time between trial groups; it is not a promise of how long a particular person will live.
The medicines act on different parts of the cancer environment. Pembrolizumab blocks PD-1, a checkpoint that can limit T-cell activity. Axitinib inhibits VEGF signaling, which supports tumor blood-vessel growth and may contribute to immune suppression within the tumor. Combining these approaches has a biological rationale, but the best choice still depends on the person's disease and circumstances.
Treatment also requires monitoring. Teams assess blood pressure, renal and hepatic function, thyroid testing, urine protein, and medications at baseline, then watch for immune-mediated toxicities and VEGF or TKI effects. Side effects, response, other health conditions, and the patient's goals can lead to dose changes or a different regimen.
Ask which regimen fits your risk group and disease pattern, and which side effects need a same-day call.
Sunridge Medical notes that diagnosis, stage, biomarkers, treatment history, medications, laboratory findings, and current health affect which treatments may be reasonable or safe. Patients should not stop or change oncology treatment without speaking with the clinicians directing their care.
Local Treatments When Disease Is Limited
Local treatment may help when there are only a few lesions, each can be treated safely, and treating them has a clear purpose, such as relieving symptoms or controlling disease at specific sites. The number and location of metastases, how the cancer has behaved, and prior treatment all matter. Stage alone does not determine whether a local approach is appropriate.
Cytoreductive nephrectomy is surgery to remove the primary kidney tumor when metastases are already present. The NCI kidney cancer treatment PDQ summary reports median overall survival of 38.1 months among patients who underwent nephrectomy, compared with 16.4 months for those who received systemic therapy alone. This comparison requires caution: patients selected for surgery may have differed from those who were not, and the results reflect older treatment eras.
Nephrectomy is therefore not an automatic first step. Many patients start with systemic therapy. Surgery may be reconsidered for selected patients whose cancer responds, those with durable oligometastatic disease, or those whose kidney mass causes bleeding, pain, obstruction, or other significant symptoms.
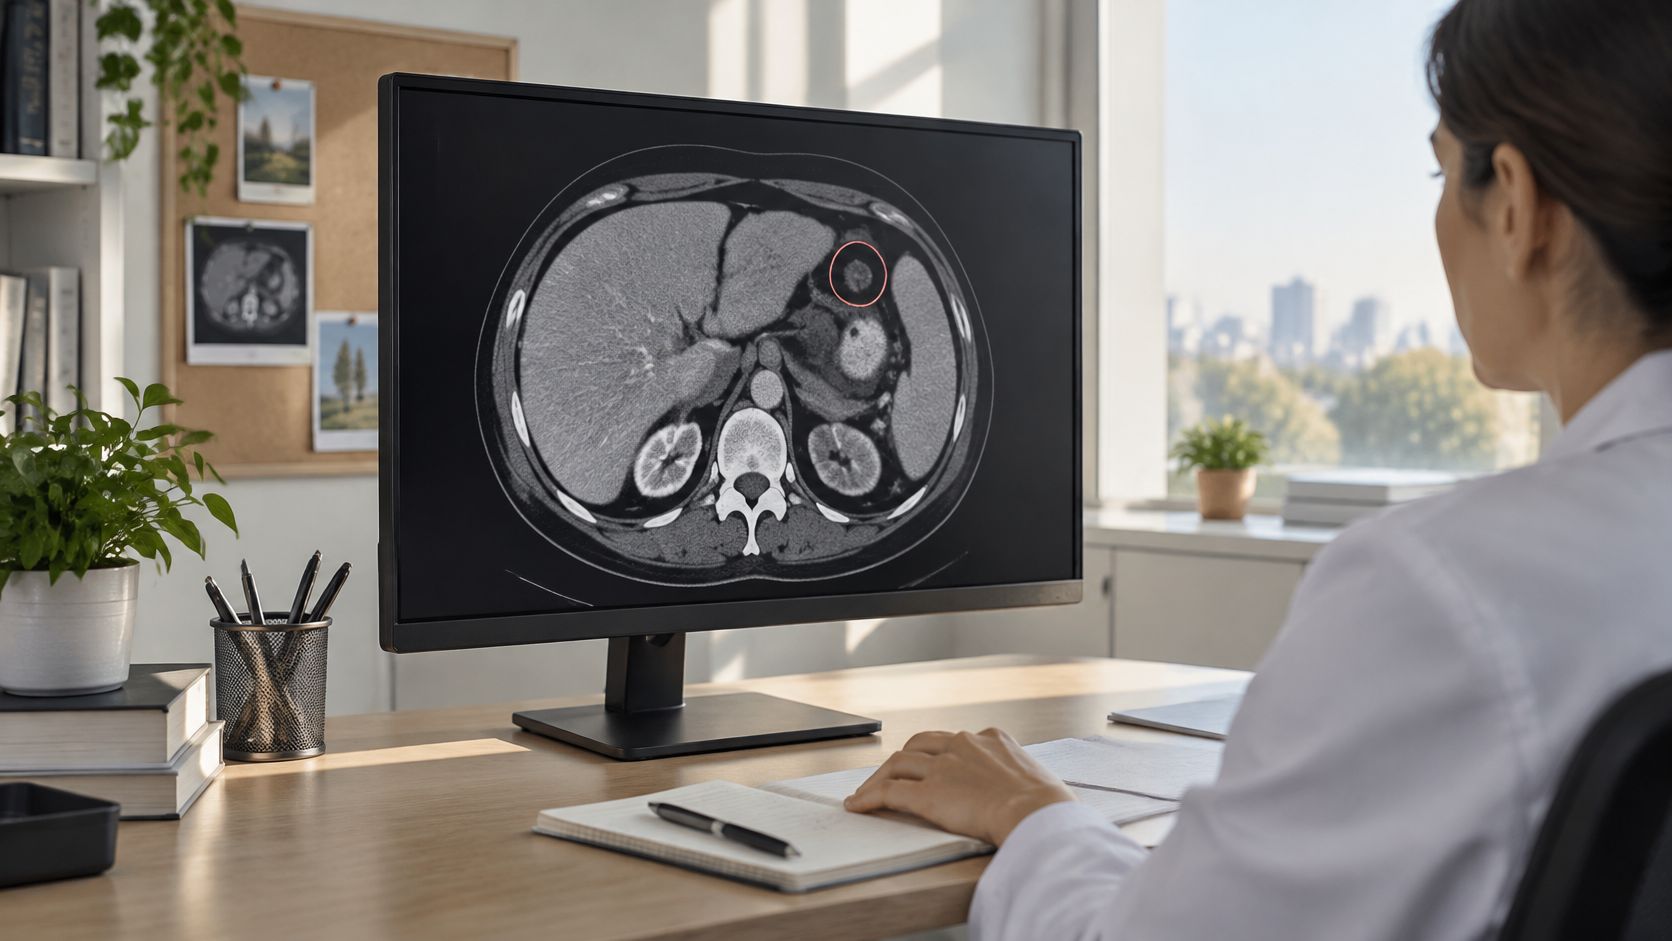
Imaging helps determine whether a local treatment is practical and what it might achieve.
Oligometastatic and oligoprogressive disease
Oligometastatic disease refers to cancer that has spread to a limited number of sites. Oligoprogressive disease describes a pattern in which a small number of lesions grow while the others remain controlled. A 2025 review of local treatment approaches in metastatic kidney cancer reports that metastasectomy, which removes metastatic tumors, and stereotactic ablative radiotherapy can provide local control, particularly for bone, lung, and brain metastases. Evidence for these approaches remains less firm than for systemic therapy. The review also reports an association between complete metastasectomy and better overall and progression-free survival compared with incomplete or no metastasectomy. Stereotactic body radiotherapy may provide lasting control and palliation.
The key question is whether the visible disease can be treated safely and usefully. Clinicians consider how many lesions there are, where they are, how long the cancer has been present, how it responded to previous treatment, the patient's functional status, and whether all visible sites can be addressed. For example, two controlled lung lesions and one growing bone lesion may lead to discussion of treating the growing site. Rapid growth across the lung, liver, bone, and brain usually points toward systemic management first.
Local treatment may delay a change in systemic therapy or control a lesion that threatens symptoms or organ function. It does not establish that the cancer has been eliminated. PD-L1 has been an unreliable predictive biomarker in renal cancer, while serum and urine biomarkers remain experimental. Decisions therefore call for more than a stage, tumor size, or single biomarker.
Questions for the tumor board can clarify the plan:
- Pathology confirmed: Is the subtype clear-cell or non-clear-cell, and has the report been reviewed?
- Disease map complete: Which sites are involved, and can every visible lesion be treated?
- Purpose defined: Would local treatment relieve symptoms, protect an organ, defer a drug change, or complement systemic therapy?
- Risk documented: What are the current IMDC group and performance status?
Options After Progression and Clinical Trial Pathways
What should happen when a scan shows growth? Progression starts a reassessment, which can reveal several different paths. A growing spot may reflect true progression, a treatment effect, a new problem, or limited growth while other sites remain controlled.
Reassessment usually includes updated imaging, review of prior drugs and response, medication and comorbidity review, organ function testing, and, when needed, confirmation of the pathology. The team can then distinguish among FDA-approved therapies, guideline-supported choices, and investigational results. These categories reflect different levels of evidence and uncertainty.
Belzutifan represents an approved option after prior treatment. A PubMed record for guidance on previously treated advanced clear-cell disease describes its superior efficacy to everolimus in the phase 3 LITESPARK-005 setting after prior immune-checkpoint and anti-angiogenic therapy. This evidence applies to a defined treatment setting and does not establish the same benefit for every kidney cancer subtype or treatment history.
Casdatifan belongs to a different category. The same guidance record reports that, at ASCO 2025, the investigational HIF-2α inhibitor casdatifan plus cabozantinib produced responses in 41% of 27 previously treated patients. This is an early signal, not definitive comparative evidence. Larger studies are needed to clarify safety, durability, and how the combination compares with other options.
HIF-2α inhibition also involves trade-offs, including anemia and oxygen-related risks. Ask how hemoglobin and oxygen symptoms would be monitored, whether medicines could interact, and when dose interruption or discontinuation might be considered. Resistance, cumulative side effects, and overall health can also change the balance among later-line treatments.
A clinical trial may be a reasonable next step. Eligibility depends on prior therapy, measurable disease, organ function, performance status, and the study's criteria.
Trial searches commonly begin with ClinicalTrials.gov and the NCI trial search. The treating oncologist can help confirm eligibility and whether the timing fits the patient's care. A trial may be worth discussing when its criteria match the cancer's histology, biomarker profile, prior treatment, or the patient's health status. Patients can review Sunridge Medical's cancer clinical trials resource and confirm potential next steps with their care team.
Long-term follow-up supports durable benefit for some immunotherapy combinations, while outcomes vary with histology, risk group, metastatic sites, prior treatment, and general health. Do not stop or change oncology treatment without speaking with the clinicians directing your care. A second opinion can help review treatment sequencing in coordination with the existing team.
Integrative Therapies Compared With the Evidence
Integrative care can support patients alongside oncology care, with the aim of addressing symptoms, treatment tolerance, and quality of life. It does not replace an oncologist, emergency care, or medically necessary cancer treatment. Before considering an option, identify what kind of evidence supports it and what question that evidence actually answers.
Demonstrated outcomes means a treatment improved a defined endpoint in studied patients. Associations, laboratory mechanisms, off-label use, supportive symptom care, and investigational approaches provide different kinds of information; they should not be described as established kidney cancer treatments.
Integrative options by evidence status and key checks
| Approach | Evidence status for kidney cancer | Key checks before use |
|---|---|---|
| Nutrition, hydration and exercise support | Supportive care; evidence mainly for symptoms and quality of life | Kidney function, electrolytes, diet restrictions |
| High-dose IV vitamin C | Investigational for cancer; not an established kidney cancer treatment | G6PD status, kidney stone history, kidney function |
| IV glutathione | Limited and preliminary; not an established cancer treatment | Product quality, kidney and liver function, medication interactions |
| Ozone therapy | Investigational for cancer; not established for kidney cancer | Route, contraindications, oncology team review |
| Insulin potentiation therapy | Experimental for cancer; not an established standard | Screening requirements, hypoglycemia risk, medication review |
Nutrition, hydration, and exercise belong in supportive care when the goal is to maintain strength, ease symptoms, support treatment tolerance, or improve quality of life. Kidney function can change what is appropriate: fluid intake, protein targets, electrolytes, supplements, and exercise intensity may need adjustment for reduced kidney function, anemia, bone metastases, blood pressure, or current drug therapy.
IV and oxidative approaches call for careful review. Before discussing high-dose IV vitamin C, ask about G6PD testing, kidney stone history, kidney function, product preparation, and possible interactions. IV glutathione raises questions about product quality, liver and kidney function, and whether antioxidant exposure could interfere with a planned regimen. Ozone therapy and insulin potentiation therapy remain investigational or experimental for cancer. Their use calls for oncology review, screening for contraindications, and clear safety monitoring.
A biological mechanism can explain how a substance acts in cells, but it cannot establish patient benefit on its own. Glutathione, for example, has antioxidant roles in cells; that fact does not show that infusions improve survival in metastatic kidney cancer.
ASCO's integrative oncology guidance distinguishes symptom-focused integrative care from cancer treatments without established evidence. Patients can ask whether a proposed therapy has been studied in kidney cancer, which outcome was measured, what the product contains, how its quality is assessed, and how it may interact with current medications. For context on how complementary approaches may fit alongside standard care, see Sunridge Medical's page on complementary cancer treatment.
Sunridge Medical individualizes care after clinical evaluation and may coordinate with existing physicians when appropriate. The therapies in a list are not automatically available or suitable for each patient. A case review can consider the cancer type and stage, prior treatment, current health, and individual goals before discussing options.
Decide Whether a Second Opinion Fits Your Situation
A second opinion is most useful when a decision depends on details that another team can verify or reinterpret. Common triggers include uncertain pathology, staging imaging that doesn't match symptoms, an unclear IMDC risk group, a proposed nephrectomy or local treatment, possible trial eligibility, or progression after prior therapy. It's also reasonable when treatment trade-offs are close and the patient wants the reasoning tested.
Preparation determines whether the review produces a concrete answer. Patients can use Sunridge Medical's cancer diagnosis second opinion page as a starting point, then assemble the records below.
Records to send before the visit
- Pathology materials: Report, subtype, grade, and slides or blocks if re-review may be needed.
- Imaging: CT, MRI, PET, or bone scan reports with actual images on disc or through a portal when possible.
- Recent laboratories: Hemoglobin, calcium, platelets, neutrophils, kidney and liver function, thyroid tests, and urine protein when available.
- Treatment history: Drug names, start and stop dates, response, side effects, surgeries, radiation, and reasons for changes.
- Medication and supplement list: Prescription drugs, over-the-counter products, vitamins, herbs, and integrative therapies.
- Written questions and goals: Symptoms that matter most, acceptable trade-offs, travel limits, and decision deadlines.
The question list should be direct. Which IMDC risk group applies, and which adverse factors are present? Is the cancer clear-cell or non-clear-cell? Which organs are involved, and is disease limited or widespread? What response would look like on scans? Which approved regimens, local treatments, or trials fit the prior therapy history, and what evidence supports each?
For patients traveling to Scottsdale or the greater Phoenix area, records should be sent in advance when possible. A case review before travel may clarify whether an in-person consultation is appropriate, what additional imaging is needed, and how scheduling can fit around oncology treatment cycles. The existing oncologist should receive updated recommendations so care stays coordinated.
Sunridge Medical welcomes stage 4 and advanced cancer patients, including out-of-state and international patients, and welcomes questions before scheduling. Sunridge offers second opinions and case review for cancer patients, care alongside oncology treatment, and treatment for advanced and difficult cases. Its Patient Care Team can answer questions and help determine the next step in a patient's cancer journey.
Suitability is determined only after individualized evaluation. Oncology care should continue unchanged while records are reviewed, unless the clinicians directing care advise otherwise. Patients who want a structured review can contact Sunridge Medical in Scottsdale, Arizona to discuss whether a consultation or second opinion is appropriate.
Sunridge Medical in Scottsdale offers individualized case review and second opinions for patients navigating stage 4 metastatic kidney cancer, including review of pathology, prior treatment, symptoms, organ function, and goals alongside existing oncology care. Patients can contact the clinic to discuss whether a consultation fits their situation, with suitability determined after clinical evaluation, by starting at Sunridge Medical.